
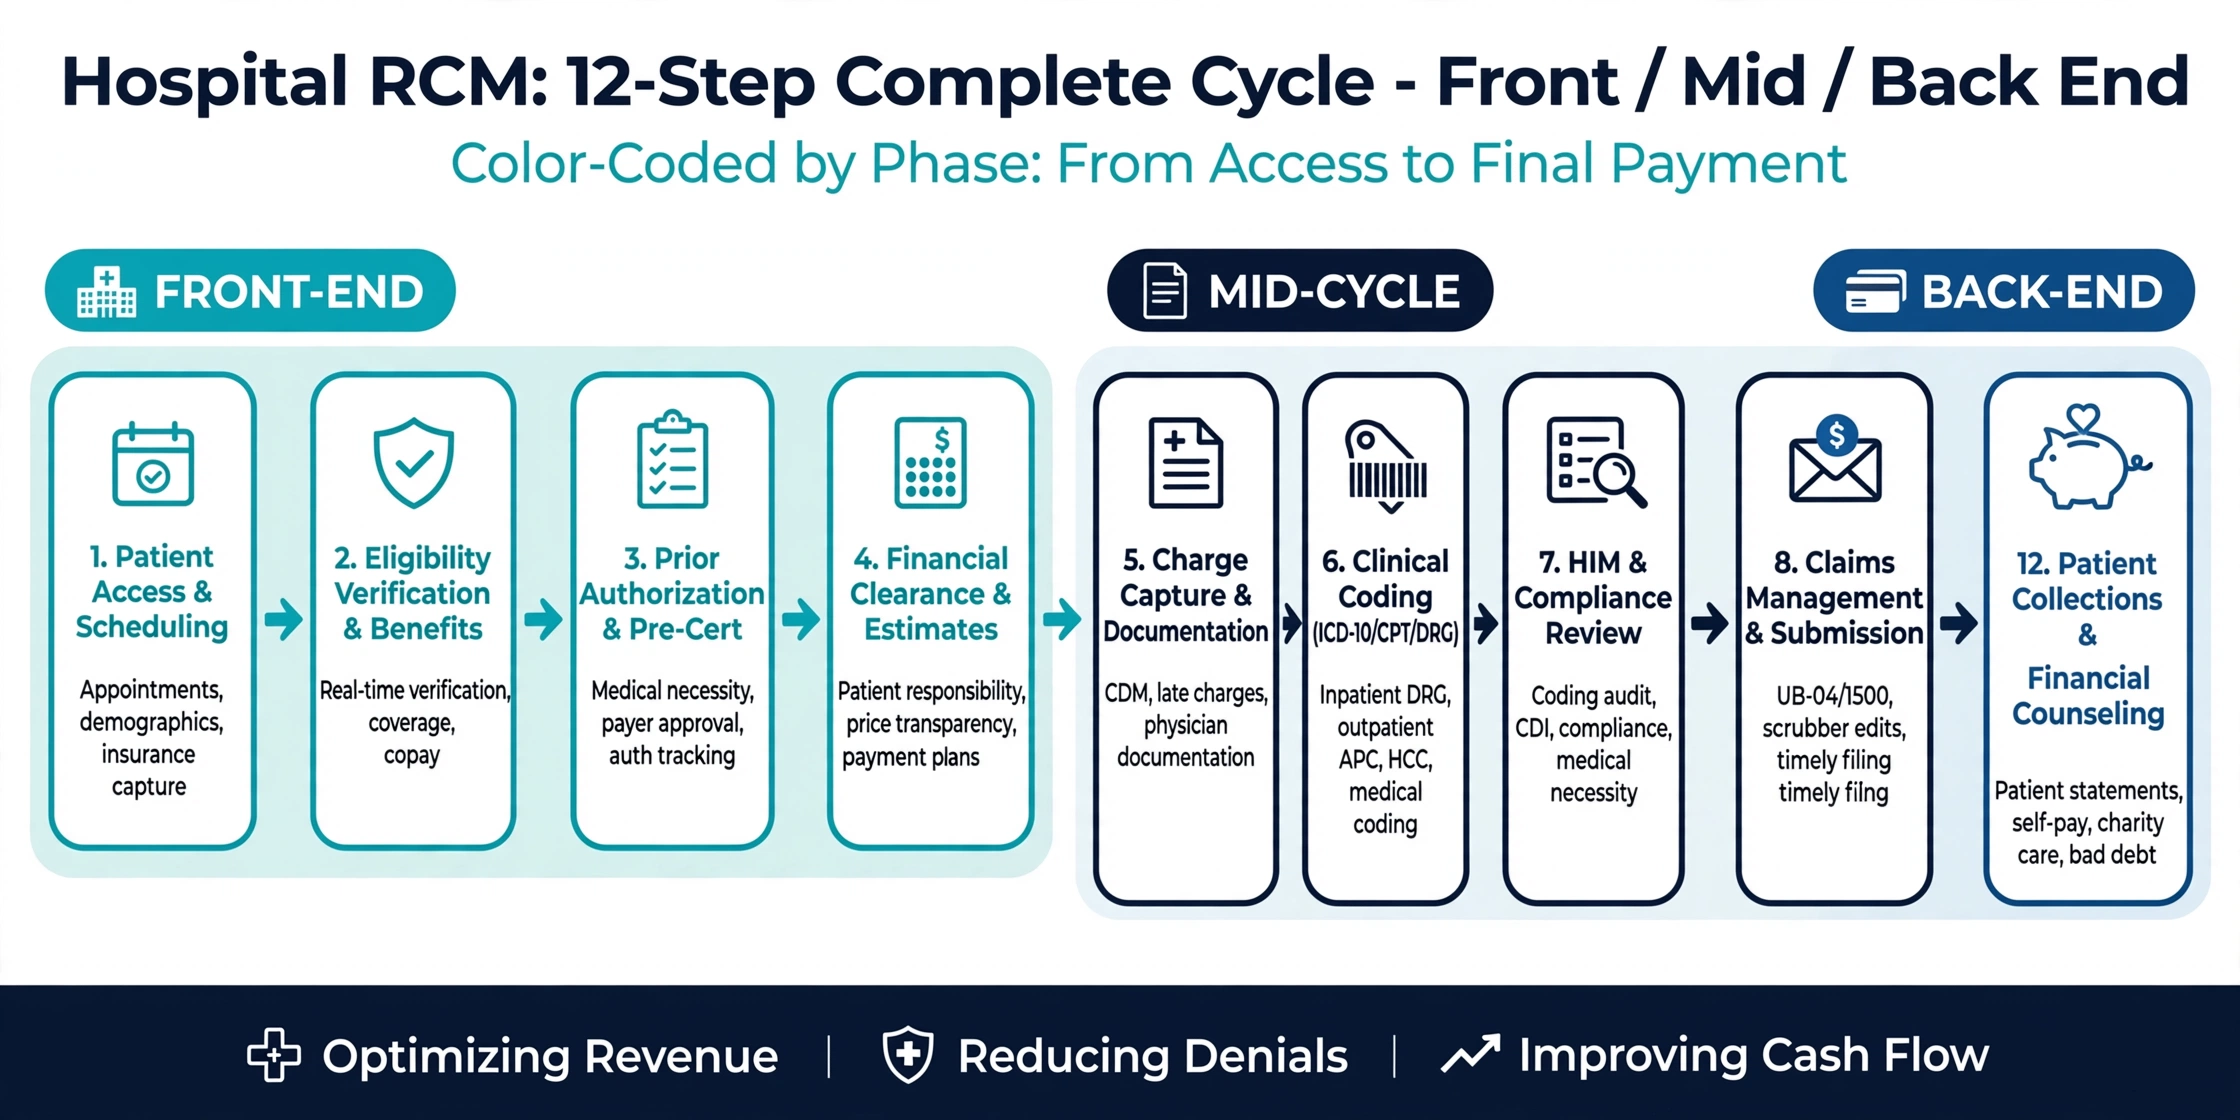
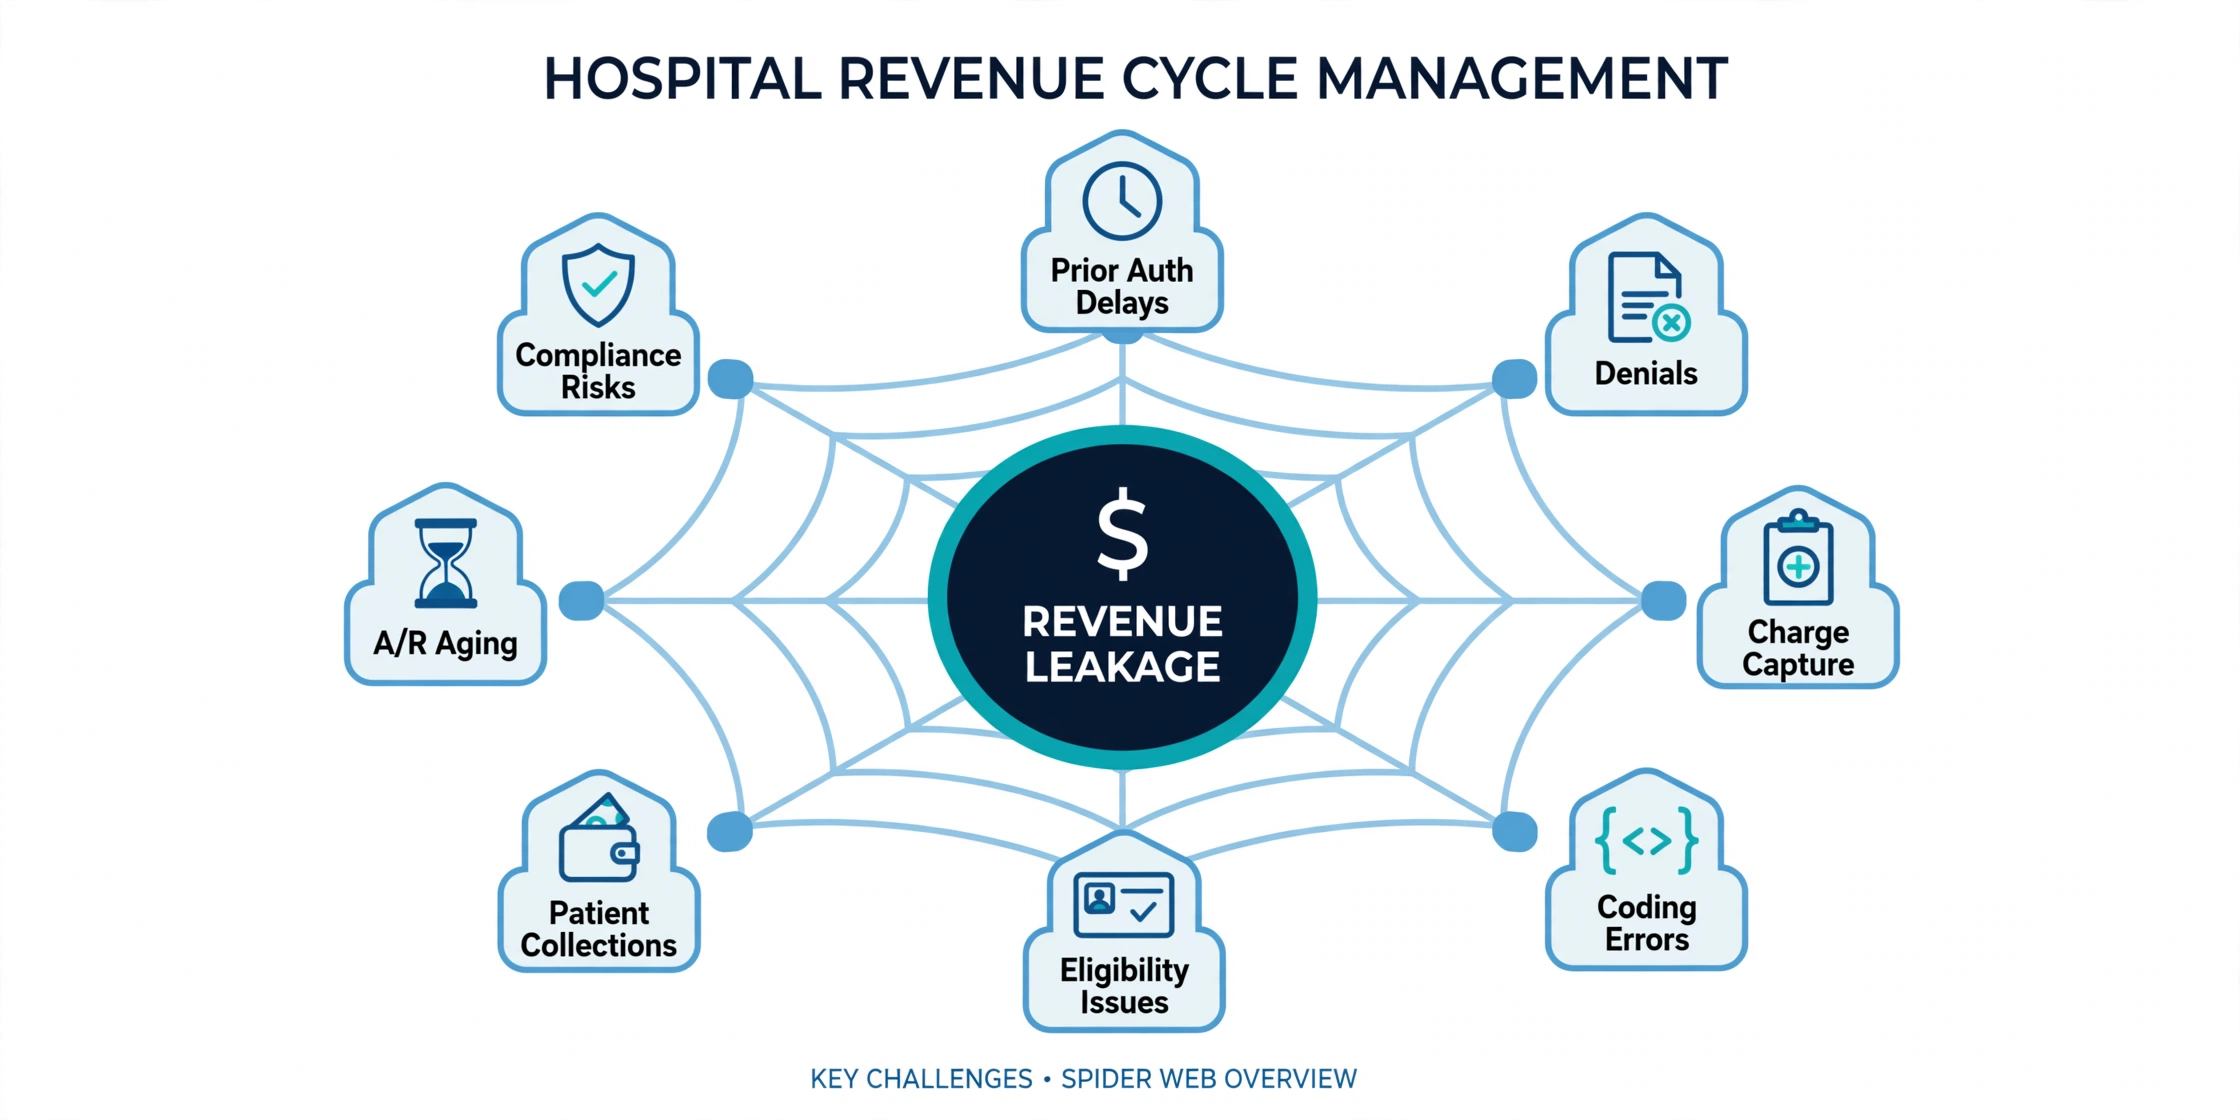
Our Hospital RCM services help healthcare organizations optimize revenue through accurate coding, claims management, compliance support, and denial prevention. We streamline complex hospital billing workflows to improve reimbursements, reduce revenue leakage, and support long-term financial performance.

Medicaid eligibility verification is the process of confirming a patient’s active enrollment and applicable coverage before rendering care. Because Medicaid is administered at the state level, this process carries more variability than most commercial or Medicare checks.
Simply seeing “active” on a state portal isn’t the full picture — providers also need to distinguish eligibility from benefit coverage, understand how Medicaid differs from prior authorization requirements, and know exactly where this step fits within the broader revenue cycle.
Verifying Medicaid coverage before the visit is one of the most effective ways to avoid denials tied to eligibility gaps, retroactive terminations, or plan reassignments — all of which are more common in Medicaid than in commercial insurance.
Early confirmation also helps your team flag patient financial responsibility where applicable, reduce billing rework, and protect cash flow from the unpredictability that often comes with state-administered coverage changes.
Because Medicaid IDs, managed care assignments, and coverage categories can change frequently, accurate intake is even more critical than with other payer types.
Front-desk staff should collect the patient’s full legal name and demographics, date of birth, Medicaid ID number, group number if applicable, insurance card details, subscriber relationship, primary and secondary coverage, and the planned date and type of service.
Once intake is complete, your team needs to validate specific details either through the state Medicaid portal or with the assigned managed care organization (MCO).
This includes active/inactive status, effective and termination dates, plan or MCO type, network participation, covered benefits, deductible if any, copay, coinsurance, benefit limitations, exclusions, referral rules, prior authorization requirements, and coordination-of-benefits status. As with commercial payers such as Aetna, electronic eligibility responses can return active coverage, effective dates, cost-sharing figures, and coordination-of-benefits data — though Medicaid responses often route through a state-specific system rather than a single national one.
Use our complete Medicaid eligibility verification checklist to confirm active enrollment, coverage dates, benefit eligibility, managed care plan assignment, patient responsibility, and service-specific requirements before care is provided. We help you verify these details upfront so you can identify coverage changes early, prevent avoidable denials, and maintain accurate Medicaid billing.
| Verification Item | What to Check | Why It Matters | Action Required |
|---|---|---|---|
| Coverage status | Active/inactive on date of service | Confirms payable service | Verify before every visit |
| Effective/termination dates | Start and end of enrollment | Medicaid eligibility can change monthly | Cross-check against DOS |
| Plan/MCO type | Fee-for-service vs. managed care | Determines billing pathway | Identify exact MCO |
| Network status | In-network with assigned MCO | Impacts reimbursement | Confirm provider enrollment |
| Covered benefits | State-specific benefit package | Avoids non-covered denials | Match against planned service |
| Cost-sharing | Copay if applicable | Most Medicaid has minimal cost-sharing | Confirm state rules |
| Benefit limitations | Visit or service caps | Prevents over-utilization denials | Check against service history |
| Authorization/referral | Required per MCO policy | Prevents authorization denials | Confirm before scheduling |
| COB status | Medicaid as payer of last resort | Prevents COB-related denials | Verify other coverage first |
A consistent, repeatable process helps your team manage Medicaid’s frequent eligibility changes without missing critical details.
The recommended sequence includes: collecting accurate patient information, validating the Medicaid ID, confirming coverage for the date of service, identifying the exact plan or MCO, confirming network participation, verifying service-specific benefits, reviewing any cost-sharing, checking authorization or referral rules, verifying COB, and documenting the result.
Many state Medicaid programs support the same HIPAA-standard 270/271 transaction pair used across the industry, though the systems processing them vary by state.
The 271 response typically returns coverage status, effective dates, benefit information, and cost-sharing details. For comparison, CMS’s HETS system accepts HIPAA-compliant 270 inquiries for Medicare FFS and returns real-time 271 responses — a useful benchmark, though most state Medicaid agencies operate their own separate eligibility systems rather than relying on HETS.
We compare Medicaid eligibility verification methods so you can understand how state portals, Medicaid managed care plans, clearinghouse transactions, and other payer channels support coverage and benefit checks. You can use this comparison to select the right verification method, confirm current enrollment accurately, and reduce coverage-related billing errors and denials.
| Verification Method | Best Use | Information Available | Advantages | Potential Limitations |
|---|---|---|---|---|
| State Medicaid portal | Routine daily checks | Enrollment, plan assignment | Direct, authoritative source | Varies significantly by state |
| 270/271 transaction | Automated high-volume checks | Standardized eligibility data | Real-time where supported | Not all states fully support it |
| Clearinghouse | Multi-payer workflows | Aggregated eligibility data | Efficient for mixed payer mix | May lag behind state updates |
| Phone verification | Complex or disputed cases | Representative-confirmed detail | Personalized clarification | Long hold times |
| Automated verification | Recurring patient checks | Standard eligibility fields | Saves staff time | Limited detail on MCO benefits |
| Manual MCO representative check | MCO-specific benefit questions | Plan-specific detail | High accuracy | Time-intensive |
Reading a Medicaid response correctly requires attention to more than the coverage status line, since MCO assignment and benefit categories often determine what’s actually billable.
Key fields to review include coverage status, MCO or plan name, effective dates, service type, cost-sharing information if applicable, out-of-pocket details, network indicators, benefit limitations, and authorization or referral flags.
A common and costly assumption is that active Medicaid enrollment automatically means a service will be reimbursed. State benefit packages, MCO-specific exclusions, and frequency limits can all affect the outcome.
Before assuming coverage, check for service-specific exclusions, visit frequency limitations, benefit maximums, medical necessity policies, network restrictions, and whether authorization is required for that particular service.
We help you identify frequent Anthem eligibility problems, including inactive coverage, member-data mismatches, plan changes, network discrepancies, and incomplete benefit information. You can address these issues before service by rechecking eligibility data, validating payer responses, and confirming unclear coverage details to reduce denials and billing delays.
| Eligibility Problem | What It Means | Claim/Revenue Risk | Recommended Solution |
|---|---|---|---|
| Inactive coverage | Enrollment lapsed or pending | Denied claim | Reverify close to DOS |
| Incorrect Medicaid ID | Wrong or outdated ID number | Rejected eligibility request | Confirm against current card |
| Wrong MCO identified | Patient reassigned to new MCO | Claim sent to wrong plan | Re-verify MCO assignment |
| Coverage terminated | Enrollment ended before DOS | Full claim denial | Check termination date pre-visit |
| Provider not enrolled with MCO | No network agreement | Reduced or denied payment | Confirm MCO enrollment status |
| Incorrect COB | Medicaid billed before other payer | Recoupment risk | Bill primary payer first |
| Missing authorization | Required MCO approval not obtained | Authorization denial | Confirm auth requirement early |
| Benefit exclusion | Service outside state benefit package | Non-covered denial | Check state-specific benefits |
| Retroactive eligibility change | Coverage adjusted after service | Delayed reimbursement | Monitor eligibility status regularly |
| Incorrect plan selected | Wrong MCO or FFS status on file | Processing errors | Confirm exact plan/MCO name |
While Medicaid cost-sharing is typically minimal or waived for many populations, some states and services do carry copays, so confirming this per state and per service category avoids surprises.
Where applicable, verify copay by service type, any state-mandated exemptions, and how in-network versus out-of-network responsibility differs, then communicate any expected costs clearly to the patient.
We help you verify Medicaid patient financial responsibility by confirming applicable copayments, deductibles, spend-down requirements, cost-sharing exemptions, and other state- or plan-specific rules before service. You can use these details to communicate allowable patient costs accurately, avoid improper collections, and maintain a cleaner billing process.
| Cost-Sharing Element | What to Verify | Example Scenario | Why Providers Need It |
|---|---|---|---|
| Copay | State-specific copay amount | $2 copay for a specialist visit | Sets accurate patient expectation |
| Exemptions | Populations exempt from cost-sharing | Pregnant patients often exempt | Prevents incorrect billing |
| Service-specific cost-sharing | Cost-sharing varies by service | Emergency services often exempt | Avoids overcharging patients |
| MCO-specific rules | Cost-sharing set by MCO contract | Different MCOs, different rules | Ensures consistent billing practice |
Medicaid managed care requires providers to be enrolled with the specific MCO a patient is assigned to — enrollment with one MCO doesn’t guarantee participation with another.
Verification should confirm provider-level, facility-level, and location-specific enrollment with the correct MCO, along with any referral restrictions tied to that plan.
Medicaid coverage isn’t uniform — it spans several structures that each carry different verification requirements.
Common categories include traditional Fee-for-Service Medicaid, Managed Medicaid through an MCO, dual-eligible Medicare-Medicaid coverage, and state-specific waiver or expansion programs, each requiring its own verification approach.
We help you identify the patient’s Medicaid coverage type and verify the specific eligibility, benefit, managed care, and service requirements that apply to their plan. You can confirm these details before care to follow the correct billing pathway, identify coverage restrictions, and prevent avoidable eligibility-related denials.
| Coverage Type | Network Requirement | Referral Risk | Authorization Consideration | Verification Priority |
|---|---|---|---|---|
| Fee-for-Service Medicaid | State-enrolled providers only | Low | Moderate | High |
| Managed Medicaid (MCO) | Strict MCO network | High | Often required | Critical |
| Dual-eligible (Medicare + Medicaid) | Medicare network + Medicaid rules | Medium | Requires MSP check | Critical |
| Waiver/expansion programs | Program-specific network | Medium | Varies by state | High |
Because MCOs frequently require prior authorization for services that Fee-for-Service Medicaid may not, building authorization checks into eligibility verification prevents costly gaps.
Confirm which services require MCO approval, who is responsible for obtaining it, effective authorization dates, approved units or visits, and any service-specific limitations before scheduling.
Managed Medicaid plans often mirror HMO-style referral requirements, making this an area where oversight easily leads to denials.
Confirm whether a PCP or specialist referral is required, MCO-specific referral rules, referral validity dates, the number of approved visits, and any restrictions on the rendering provider.
Medicaid is generally the payer of last resort, meaning any other applicable insurance must be billed first. Getting this order wrong is a frequent and preventable source of denials and recoupments.
Confirm primary versus secondary status, apply Medicare secondary payer rules for dual-eligible patients, account for other commercial coverage, and understand the patient impact when COB information is incorrect.
We help you determine whether Medicaid is primary or secondary by checking other active insurance, coordination of benefits, managed care enrollment, and applicable payer sequencing requirements. You can establish the correct billing order before claim submission to reduce COB-related denials, payment delays, and incorrect patient balances.
| Scenario | Likely Verification Issue | What Staff Should Confirm | Recommended Action |
|---|---|---|---|
| Medicaid + commercial insurance | Medicaid should be secondary | Commercial plan billed first | Confirm and bill primary first |
| Dual-eligible (Medicare + Medicaid) | Medicare typically primary | MSP status and Medicaid as secondary | Apply correct billing order |
| Outdated COB on file | Old insurance still listed | Current active coverage sources | Update COB before billing |
| Multiple state programs | Overlapping program enrollment | Which program is currently active | Confirm with state portal |
Medicaid benefit packages vary by state and service line, so a general eligibility check often isn’t sufficient for specialty care.
This applies across office visits, specialist visits, behavioral health, physical therapy, occupational therapy, speech therapy, ABA therapy, diagnostic imaging, laboratory services, surgery, DME, home health, and telehealth — each with its own state-specific coverage rules and MCO limitations.
We help you verify Medicaid benefits for the specific service being provided, including coverage limits, visit or frequency restrictions, authorization requirements, and managed care plan rules. You can confirm these details before treatment to identify coverage limitations early, prevent non-covered services, and reduce avoidable claim denials.
| Service Category | Benefits to Verify | Common Limitation | Authorization/Referral Check | Provider Risk |
|---|---|---|---|---|
| Behavioral health | Session limits, state coverage | Annual visit caps | Often required by MCO | Denial if cap exceeded |
| ABA therapy | Covered hours, provider enrollment | State-specific hour limits | Frequently required | Non-covered hours |
| Diagnostic imaging | Coverage, MCO network | Pre-cert for advanced imaging | Frequently required | Authorization denial |
| DME | Coverage, rental vs. purchase | Quantity/frequency limits | Often required | Non-covered equipment |
| Home health | Visit frequency, eligibility criteria | State-specific caps | Often required | Denied visits beyond cap |
Medicaid’s frequent eligibility changes make certain verification mistakes especially costly if left unaddressed.
Common errors include verifying too early before scheduling changes occur, failing to reverify close to the date of service, checking only active/inactive status, overlooking MCO-specific benefits, missing MCO reassignments, entering incorrect demographics, skipping network enrollment checks, missing COB updates, failing to document verification, and assuming authorization from eligibility status alone.
We help you identify Medicaid verification errors that can result in eligibility denials, incorrect payer sequencing, non-covered services, delayed reimbursement, and unnecessary claim rework. You can catch these issues before care is delivered to protect revenue, reduce avoidable A/R, and maintain a more consistent Medicaid billing workflow.
| Staff Error | Possible Consequence | Revenue-Cycle Impact | Prevention Strategy |
|---|---|---|---|
| Checked too early | MCO reassignment before DOS | Claim sent to wrong plan | Reverify closer to visit |
| Only checked active status | Missed benefit exclusions | Non-covered denial | Full benefit verification |
| Incorrect demographics | Rejected eligibility request | Processing delay | Cross-check Medicaid card |
| Missed authorization | Service delivered without MCO approval | Authorization denial | Confirm auth during verification |
| No documentation | No record of verification | Difficulty appealing denials | Standardized documentation log |
New patients require a full benefit workup, while returning patients need focused checks for changes that may have occurred since their last visit — which happens more often under Medicaid than commercial coverage.
Key triggers for returning patients include MCO reassignment, redetermination cycles, new eligibility categories, changes in benefit coverage, and updated Medicaid cards.
Given how frequently Medicaid eligibility can shift, establishing clear reverification checkpoints is especially important for this payer type.
Recommended checkpoints include at scheduling, shortly before the appointment, on the date of service, after any known eligibility redetermination, following MCO reassignment, and before high-cost or recurring treatments.
We help you build a Medicaid verification timeline that checks eligibility during scheduling, confirms plan and benefit details before service, and revalidates coverage close to the date of care. You can use this workflow to catch enrollment or managed care changes early, prevent coverage-related denials, and keep claims moving without unnecessary delays.
| Verification Stage | Timing | What to Check | Staff Action | Risk Prevented |
|---|---|---|---|---|
| At scheduling | Initial contact | Basic enrollment status | Confirm active coverage | Wasted scheduling effort |
| Before appointment | 24–72 hours prior | Full benefits, MCO assignment | Detailed verification | Day-of surprises |
| Date of service | Day of visit | Real-time status | Final confirmation | Coverage lapses |
| After redetermination | As reported/expected | Updated eligibility category | Full reverification | Claim mismatches |
| MCO reassignment | As it occurs | New MCO network/benefits | Confirm new enrollment | Wrong-payer billing |
High-cost procedures carry greater financial and compliance risk under Medicaid, particularly given stricter authorization requirements from many MCOs.
For these cases, confirm detailed benefits, MCO authorization status, network enrollment, benefit maximums, any applicable cost-sharing, and prepare documentation with reference numbers to support the claim if questioned later.
Many Medicaid denial categories stem directly from front-end verification gaps, making this step one of the highest-impact areas for improvement.
Verification helps prevent denials tied to inactive enrollment, non-covered services, incorrect COB order, missing MCO authorization, network enrollment issues, incorrect patient information, and MCO mismatches.
We help you identify common Medicaid denial scenarios, including inactive eligibility, incorrect managed care assignment, missing authorization, COB conflicts, and service-specific coverage restrictions. You can apply the right preventive verification steps before service to reduce avoidable denials, claim rework, and reimbursement delays.
| Denial Scenario | Root Cause | What Should Have Been Verified | Corrective Action | Preventive Action |
|---|---|---|---|---|
| Inactive coverage denial | Enrollment lapsed before DOS | Effective/termination dates | Appeal with updated info | Reverify closer to DOS |
| Non-covered service | Service outside state benefit package | Benefit details | Adjust billing or appeal | Verify service-specific benefits |
| COB denial | Medicaid billed before other payer | Payer order | Rebill correct payer order | Confirm COB each visit |
| Authorization denial | No prior MCO approval obtained | Authorization requirement | Retroactive auth request | Confirm auth before service |
| Wrong-MCO denial | Claim sent to prior MCO | Current MCO assignment | Rebill correct MCO | Reverify MCO before service |
Thorough documentation is especially valuable with Medicaid, where retroactive eligibility changes and audits are more common.
Strong records include the date and time of verification, method used, representative name if applicable, reference number, coverage dates, confirmed benefits, patient responsibility if any, authorization or referral details, and electronic response records or staff notes.
When state portal data conflicts with what the patient reports, resolving it before billing helps avoid denials and recoupment risk.
Steps include rechecking demographics, validating the Medicaid card, contacting the state agency or MCO directly, asking the patient about recent eligibility changes, checking for an alternate program or MCO, documenting the conflict, and holding nonurgent billing until resolved.
Patients enrolled in both Medicare and Medicaid require careful attention to payer order and program-specific rules.
Key areas include understanding Medicare Part A and B interactions, applying Medicare secondary payer considerations, verifying Medicare Advantage details separately when applicable, and confirming Medicaid’s role as the secondary or wraparound payer. CMS notes that HETS applies specifically to Medicare Fee-for-Service eligibility, and that Medicare Advantage eligibility must be verified with the applicable plan — a distinction that matters for dual-eligible patients whose Medicaid benefits work alongside either Medicare structure.
Medicaid eligibility administration differs significantly from state to state, making a single national workflow impractical for this payer type.
Considerations include the distinction between Fee-for-Service Medicaid and Managed Medicaid, use of the applicable state Medicaid portal, eligibility effective dates, MCO plan assignment, provider enrollment and network participation within each state’s program, and reverification frequency tailored to that state’s redetermination cycle.
While the fundamentals of eligibility verification stay consistent, Medicaid’s structure differs meaningfully from Medicare and commercial insurance, and understanding these differences helps set realistic expectations for turnaround and complexity.
This section can be expanded with state-specific Medicaid subsections, along with comparisons to commercial payers such as Cigna, Aetna, UnitedHealthcare, Blue Cross Blue Shield, Humana, Kaiser Permanente, Molina Healthcare, Centene, and Anthem/Elevance, many of which also administer Managed Medicaid plans.
We compare Medicare, Medicaid, and commercial insurance verification to help you understand how eligibility rules, benefit structures, cost-sharing, network requirements, and payer processes differ. You can use this comparison to follow the correct verification workflow for each coverage type, prevent billing errors, and reduce avoidable claim denials.
| Area | Medicare | Medicaid | Commercial Insurance | Key Provider Consideration |
|---|---|---|---|---|
| Verification method | HETS 270/271 | State portal/MCO system | Payer portal/270-271 | Different systems per payer type |
| Network rules | FFS: none; MA: plan-specific | MCO-specific, state-governed | Plan-specific | Confirm MCO network separately |
| Reverification frequency | Annually / per event | Frequent, state redetermination cycle | Per benefit year | Track state-specific timelines |
| Authorization complexity | Moderate | Often high, MCO-dependent | Varies by plan | Confirm per MCO/state |
A clearly defined workflow keeps staff aligned and reduces the risk of gaps between scheduling and service delivery, especially given how often Medicaid details can shift.
A typical flow looks like: Patient Scheduled → Insurance Information Collected → Eligibility Checked → MCO/Benefits Verified → Network Confirmed → Authorization/Referral Checked → Patient Responsibility Identified (if any) → Verification Documented → Patient Informed.
We help you define responsibility for each Medicaid verification step, from checking active eligibility and managed care enrollment to confirming benefits, authorization requirements, COB, and patient responsibility. You can use this matrix to assign clear ownership, prevent missed verification tasks, and maintain a consistent pre-service workflow.
| Task | Front Desk | Eligibility Team | Billing Team | Authorization Team | When Completed |
|---|---|---|---|---|---|
| Collect patient info | ✔ | At scheduling | |||
| Verify active enrollment | ✔ | Before appointment | |||
| Confirm MCO and benefits | ✔ | Before appointment | |||
| Check MCO authorization | ✔ | Before service | |||
| Document verification | ✔ | ✔ | Throughout process |
Thorough Medicaid verification reduces confusion for patients who may already be navigating complex enrollment and redetermination processes.
Benefits include fewer unexpected bills, greater clarity around any applicable cost-sharing, earlier identification of coverage or MCO issues, and smoother communication between the practice and patient overall.
We help you strengthen Medicaid eligibility verification to reduce coverage-related denials, prevent billing rework, and identify payer or managed care requirements before services are provided. You can turn accurate verification into faster reimbursement, lower administrative costs, cleaner claims, and a more predictable revenue cycle.
| Benefit | Operational Impact | Financial Impact | Patient Impact |
|---|---|---|---|
| Fewer denials | Less rework for billing team | Faster reimbursement | Fewer billing disputes |
| Correct MCO identification | Smoother claims routing | Reduced recoupment risk | Fewer coverage confusion issues |
| Documented verification | Easier appeals process | Recovered revenue on disputed claims | Increased trust in practice |
Consistent quality control is essential given how frequently Medicaid eligibility and MCO assignments can change.
Core components include daily verification queues, unverified-patient reports, exception management for flagged discrepancies, periodic verification and documentation audits, denial feedback loops, ongoing staff training, and regularly updated state-specific SOPs.
Monitoring the right metrics helps identify where Medicaid verification breakdowns occur most often, given the added complexity of state and MCO variability.
Metrics worth tracking include the percentage of scheduled patients verified, verification completion before the date of service, eligibility-related and COB-related denial rates, MCO-reassignment error rate, authorization-related front-end issues, turnaround time, and unverified account volume.
| KPI | What It Measures | Why It Matters | Improvement Action |
|---|---|---|---|
| % patients verified | Coverage of verification process | Identifies workflow gaps | Expand verification queue capacity |
| Denial rate (eligibility) | Front-end verification accuracy | Direct revenue impact | Targeted staff retraining |
| MCO-reassignment errors | Accuracy of MCO tracking | Prevents wrong-payer billing | Increase reverification frequency |
| Unverified account volume | Backlog size | Signals resource strain | Reassign or outsource overflow |
Given the state-by-state complexity of Medicaid, many practices reach a point where outsourcing becomes more efficient than maintaining full in-house expertise.
Common triggers include high patient volume, limited front-desk staffing, rising eligibility-related denials, multi-state operations, MCO-specific benefit complexity, staff turnover, and a growing verification backlog.
Choosing between in-house and outsourced Medicaid verification depends heavily on how much state-specific and MCO-specific expertise your practice can maintain internally.
Key comparison points include staffing and training requirements, depth of state and MCO expertise, scalability during volume or redetermination surges, quality control processes, workflow consistency, overall cost, and coverage continuity during staff absences.
We compare in-house and outsourced Medicaid verification so you can evaluate staffing needs, state-specific workflows, managed care checks, turnaround time, and administrative workload. You can choose the right approach to improve verification accuracy, reduce eligibility-related denials, and maintain a more efficient Medicaid revenue cycle.
| Area | In-House Team | Outsourced Team | Provider Consideration |
|---|---|---|---|
| Staffing | Requires hiring/training | Ready-made expertise | Faster ramp-up with outsourcing |
| State/MCO expertise | Limited to internal experience | Broad, multi-state experience | Fewer errors across state lines |
| Scalability | Constrained by headcount | Flexible capacity | Easier to handle redetermination surges |
| Cost | Fixed salary/benefits cost | Variable, usage-based cost | Depends on practice size |
| Coverage during absence | Gaps during turnover/leave | Continuous coverage | Reduces backlog risk |
House of Outsourcing provides end-to-end Medicaid eligibility and benefits verification designed around each state’s specific requirements and MCO structures.
Our support spans Fee-for-Service and Managed Medicaid verification, dual-eligible Medicare-Medicaid checks, patient responsibility confirmation where applicable, MCO network status review, authorization and referral identification, COB verification, and thorough documentation integrated with your existing billing workflows.
House of Outsourcing brings more than a decade and a half of hands-on revenue cycle experience, including deep familiarity with the state-by-state nuances that make Medicaid verification uniquely challenging.
Our team understands MCO-specific workflows, handles complex benefit and redetermination scenarios with precision, and supports front-end revenue-cycle operations through quality-focused, scalable processes.
Providers trust House of Outsourcing because our team combines state and MCO-specific expertise with consistent documentation standards and a genuine focus on preventing denials before they happen.
We reduce administrative workload for internal staff, support broader revenue-cycle goals, and scale alongside your organization as patient volume and multi-state complexity increase.
Before every appointment, confirm: Is enrollment active? Is it valid for the date of service? Is the correct MCO identified? Is the provider enrolled with that MCO? Is the requested service covered under the state benefit package?
Also confirm: Is any cost-sharing applicable? Is prior authorization required? Is a referral needed? Are there benefit or frequency limits? Is COB accurate, with Medicaid billed as payer of last resort? And finally, has the verification been properly documented?
Medicaid eligibility can be verified through the applicable state Medicaid portal, a 270/271 electronic transaction where supported, a clearinghouse, or by phone with the state agency or MCO.
At minimum, at scheduling and again shortly before the date of service, with additional checks after any known redetermination or MCO reassignment.
Patient demographics, Medicaid ID number, insurance card details, and the planned date and type of service.
No, active enrollment doesn’t guarantee that a specific service is covered under the state’s benefit package or the assigned MCO’s rules.
Through the state Medicaid portal, the MCO’s provider portal, or by contacting the MCO directly, since cost-sharing rules vary by state and population.
Authorization requirements should be confirmed with the assigned MCO as part of the same verification process, since Fee-for-Service and Managed Medicaid often differ.
Nonurgent services should be held until the discrepancy is resolved, and the conflict should be documented for follow-up with the state or MCO.
Yes, returning patients should be reverified regularly, since Medicaid eligibility and MCO assignments can change more frequently than with other payer types.
By confirming that Medicaid is billed as the payer of last resort, after any applicable commercial or Medicare coverage has been billed first.
Yes, many practices outsource Medicaid verification specifically because of the added complexity of state and MCO-specific rules.
Get a free assessment from our billing experts
