


Our General Surgery Medical Billing services help practices manage complex surgical coding, documentation requirements, payer guidelines, and reimbursement challenges. We optimize claims, reduce denials, and improve collections through efficient revenue cycle management.

General Surgery Billing Guide: CPT Coding, Modifiers & Reimbursement Rules for 2026
When you are owner of a general surgery practice, you already know the pressure. Between appendectomies, laparoscopic cholecystectomies, hernia repairs, bowel resections, and a steady stream of trauma and emergency cases, your OR never stops, and neither does the billing complexity that follows every case.
General surgery medical billing is one of the most technically demanding areas in surgical coding. The global surgical package rules, concurrent care billing, assistant surgeon charges, the correct use of nearly a dozen modifiers, the distinction between laparoscopic and open approaches, and the ever-present prior authorization requirements combine to create a revenue cycle that demands specialist-level knowledge to manage correctly.
This guide is written for US general surgeons, surgical practice managers, hospital billing departments, and administrators who want a thorough, up-to-date, and actionable reference for general surgery billing.
What Makes General Surgery Billing Uniquely Challenging?
Compared to office-based specialties like nephrology billing or pediatric medical billing, general surgery billing operates in a fundamentally different environment. Every procedure carries a global surgical period. Every case involves operative report documentation that must precisely justify the CPT codes billed. And every surgical encounter can involve multiple providers, the primary surgeon, an assistant surgeon, the anesthesiologist, each of whom bills separately with their own rules.
Here are the core factors that distinguish your practice general surgery medical billing from other specialties:
- The Global Surgical Package: Every surgical CPT code carries a global period 0, 10, or 90 days, during which all routine pre-operative and post-operative care is bundled into the surgical reimbursement. Billing separately for included services without the correct modifier is one of the most common compliance violations in surgical billing.
- Laparoscopic vs. Open Approach: The surgical approach fundamentally changes the CPT code. A laparoscopic cholecystectomy (47562) and an open cholecystectomy (47600) are completely different codes with different reimbursement rates.
- Multiple Procedures in One Session: General surgeons frequently perform multiple procedures in a single operative session. Billing all of them correctly, understanding which are separately billable and which must be bundled, requires mastery of CCI edits and the correct application of modifier -51.
- Emergency vs. Elective Coding: Emergency surgeries, trauma cases, and unplanned operative interventions carry different coding and documentation requirements than elective procedures. Billing emergency cases incorrectly is a common source of denied claims.
- Assistant Surgeon and Co-Surgeon Billing: When a surgical assistant or co-surgeon participates, each has their own billing rules, modifier requirements (-80, -81, -82, -62), and payer-specific restrictions.
- High Prior Authorization Burden: Elective general surgery procedures including hernia repairs, cholecystectomies, bariatric surgery, and bowel resections, almost always require prior authorization from commercial payers and Medicare Advantage plans.
The Global Surgical Package Foundation of General Surgery Billing
No topic is more central to general surgery billing services than the global surgical package. Understanding exactly what is, and is not included in the global period is the single most important knowledge area for your in-house general surgery billing team.
What is the Global Surgical Package?
The global surgical package is a bundled payment concept established by CMS that defines what services are included in the reimbursement for a surgical procedure. When you bill a surgical CPT code, the payer assumes the global package covers all of the following, and will not pay separately for them unless you use the correct modifiers:
- The pre-operative evaluation on the day of surgery (and one day before for major procedures)
- The intraoperative services — the surgery itself
- All routine post-operative care provided within the global period
- Complications that do not require a return trip to the operating room
- Typical follow-up visits during the global period
Global Period Lengths in General Surgery Medical Billing
| Global Period | What It Covers | Examples in General Surgery | Post-Op Visit Policy |
|---|---|---|---|
| 0-Day Global | Day of surgery only | Simple excisions, small skin procedures | No separate post-op visit billing |
| 10-Day Global | Surgery day + 10 days after | Minor procedures, skin lesion removal, port placement | Routine follow-up bundled for 10 days |
| 90-Day Global | Surgery day + 90 days after | Major surgery: appendectomy, cholecystectomy, hernia repair, colectomy, mastectomy | All routine post-op care bundled for 90 days |
| MMM (Maternity) | Obstetric procedures only | N/A for general surgery | Governed by separate OB package rules |
| XXX (No Global) | No global period applies | Radiology, diagnostic services, most E/M codes | Bill each service separately |
Essential CPT Codes for General Surgery Medical Billing
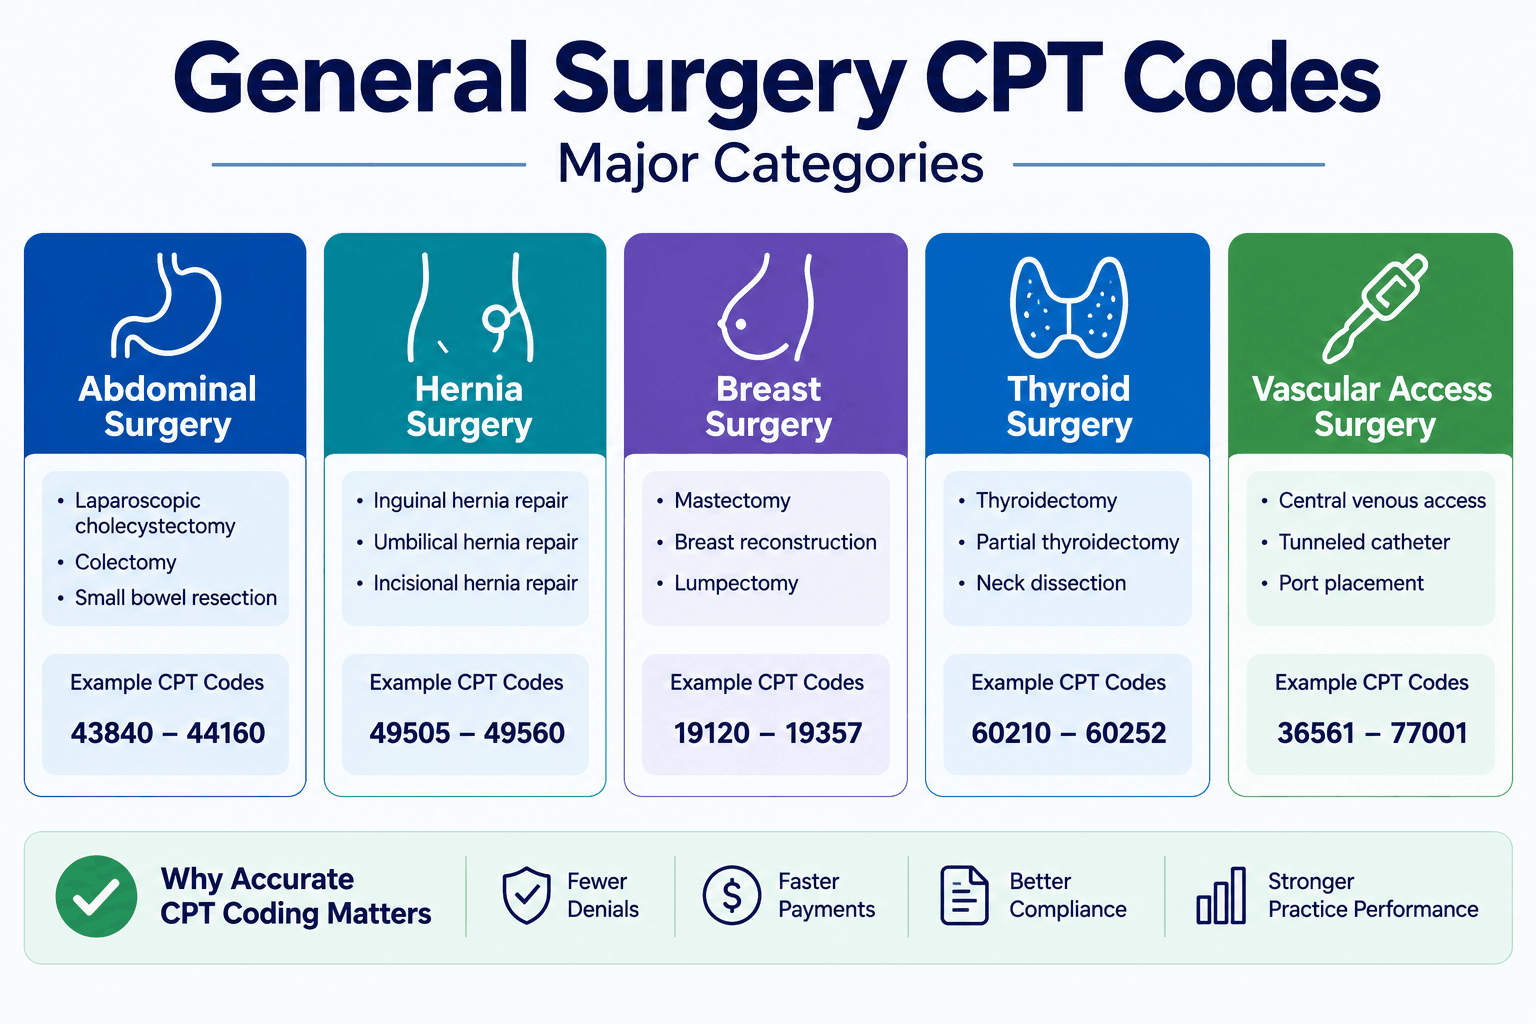
General surgery CPT codes span a broad range of procedures, from common abdominal and laparoscopic surgeries to breast surgery, hernia repairs, vascular access, and trauma cases. Here are the most important code categories and specific codes your billing team must know.
Laparoscopic & Abdominal Surgery CPT Codes
| CPT Code | Procedure Description | Key Billing Note |
|---|---|---|
| 47562 | Laparoscopic cholecystectomy | Most common general surgery code; requires complete op report documenting laparoscopic approach |
| 47600 | Open cholecystectomy | Use ONLY when open approach documented; do NOT use if laparoscopic |
| 44950/44960 | Appendectomy (incidental/complicated) | 44950 = incidental; 44960 = complicated/ruptured with abscess |
| 44204 | Laparoscopic colectomy, partial | Distinct from open colectomy 44140; approach must be documented |
| 44140 | Open colectomy, partial | Use for open partial colon resection with anastomosis |
| 44145 | Open colectomy with coloproctostomy | Low anterior resection — document extent of resection clearly |
| 44180 | Laparoscopic enterolysis (lysis of adhesions) | Can be separately billable when performed as the primary procedure |
| 49320 | Laparoscopic diagnostic — abdomen, peritoneum | Use for diagnostic lap; if therapeutic procedure performed, bill that code instead |
Hernia Repair CPT Codes for General Surgery Billing Services
Hernia repair is among the highest-volume procedures in general surgery. Correct coding requires documenting hernia type (inguinal, umbilical, ventral, incisional, femoral), laterality, whether it is initial or recurrent, and the repair approach (laparoscopic vs. open).
| CPT Code | Hernia Repair Procedure | Critical Documentation Points |
|---|---|---|
| 49505 | Open inguinal hernia repair, initial, age 5+ (reducible) | Document: initial vs. recurrent, patient age, reducible/incarcerated/strangulated |
| 49507 | Open inguinal hernia repair, initial, with mesh (reducible) | Add mesh documentation; mesh codes may be billable separately depending on payer |
| 49520 | Open inguinal hernia repair, recurrent (reducible) | Must document prior hernia repair history; ‘recurrent’ requires prior surgery evidence |
| 49560 | Open incisional hernia repair, initial (reducible) | Distinguish from ventral; document location and size |
| 49565 | Open incisional hernia repair, recurrent | Prior incisional repair must be documented |
| 49585 | Open umbilical hernia repair, age 5+ (reducible) | Age and reducibility status must be documented |
| 49650 | Laparoscopic inguinal hernia repair, initial | Most frequently billed laparoscopic hernia code; requires laparoscopic approach documentation |
| 49652 | Laparoscopic ventral, umbilical, or incisional hernia repair, initial | Document size, approach, and whether mesh was used |
Breast Surgery CPT Codes
| CPT Code | Procedure | Billing Note |
|---|---|---|
| 19301 | Mastectomy, partial (lumpectomy, tylectomy, quadrantectomy) | Document exact extent of resection; sentinel node biopsy billed separately (38792/38900) |
| 19302 | Partial mastectomy with axillary lymphadenectomy | Includes axillary dissection — do NOT separately bill axillary node codes |
| 19303 | Simple complete mastectomy | Document simple complete vs. modified radical — significantly different codes |
| 19305 | Modified radical mastectomy | Includes pectoral muscle and axillary nodes — document all included structures |
| 19307 | Radical mastectomy, including pectoral muscles and thoracic nodes | Full radical; requires complete operative documentation of all structures removed |
| 19125 | Excision of breast lesion identified by preoperative placement of radiological marker | Bill wire localization separately — requires radiology coordination |
Thyroid, Parathyroid & Endocrine Surgery Codes
| CPT Code | Procedure | Key Note |
|---|---|---|
| 60210 | Partial thyroid lobectomy | Document unilateral; distinguish from total and completion thyroidectomy |
| 60220 | Total thyroid lobectomy with isthmus | Unilateral total lobe removal — document clearly |
| 60240 | Thyroidectomy, total | Complete bilateral removal; most common thyroid surgery code |
| 60252 | Total thyroidectomy for malignancy | Requires cancer diagnosis; often requires central neck dissection coded separately |
| 60500 | Parathyroidectomy or exploration of parathyroid | For hyperparathyroidism; document number of glands explored |
| 60512 | Parathyroid autotransplantation — add-on | Add-on code to primary parathyroid procedure; cannot be billed alone |
Vascular Access, Wound Care & Other Common General Surgery CPT Codes
| CPT Code | Procedure | Billing Note |
|---|---|---|
| 36556 | Insertion of non-tunneled central venous catheter, age 5+ | Bill 36556 for non-tunneled; 36558 for tunneled |
| 36558 | Insertion of tunneled centrally inserted central venous catheter (CVC) | Tunneled vs. non-tunneled distinction is critical — different code, different RVU |
| 36570 | Insertion of peripherally inserted central venous catheter (PICC) | Document age and approach; imaging guidance billed separately |
| 10140 | Incision and drainage (I&D) of hematoma, seroma, or fluid collection | Simple I&D; document size and content of collection |
| 11042-11047 | Debridement codes — subcutaneous, fascia, muscle | Bill by depth and surface area; use add-on codes 11045-11047 for additional sq cm |
| 49000 | Exploratory laparotomy | Used when no specific intraabdominal procedure performed — requires complete documentation |
| 49021 | Drainage of peritoneal abscess or localized peritonitis, open | Distinguish from percutaneous drainage; document open approach |
ICD-10 Diagnosis Codes for Your General Surgery Medical Billing
We know that accurate ICD-10-CM coding is the clinical backbone of your general surgery claim. Every CPT procedure code must be supported by a diagnosis code that demonstrates medical necessity. Using unspecified or mismatched diagnosis codes is one of the most reliable ways to trigger a medical necessity denial.
| ICD-10 Code | Diagnosis Description | Common Associated Procedure |
|---|---|---|
| K80.20 | Calculus of gallbladder without cholecystitis, without obstruction | Laparoscopic cholecystectomy (47562) |
| K81.0 | Acute cholecystitis | Emergent laparoscopic or open cholecystectomy (47562/47600) |
| K35.2 | Acute appendicitis with generalized peritonitis | Appendectomy (44960) — ruptured/complicated |
| K37 | Unspecified appendicitis | Appendectomy (44950) — use K37 only when appendicitis not further specified |
| K40.90 | Unilateral inguinal hernia, initial encounter, without obstruction | Inguinal hernia repair (49505/49650) |
| K43.0 | Incisional hernia with obstruction, without gangrene | Incisional hernia repair (49560/49565) — document obstruction |
| C50.911 | Malignant neoplasm of right breast, unspecified | Mastectomy (19303/19305) — specify laterality with RT/LT modifier |
| D13.39 | Benign neoplasm of other parts of small intestine | Small bowel resection (44120) — document benign vs. malignant |
| E04.1 | Nontoxic single thyroid nodule | Thyroid lobectomy (60220) |
| C73 | Malignant neoplasm of thyroid gland | Total thyroidectomy for malignancy (60252) |
| K57.20 | Diverticulosis of large intestine with perforation, without abscess | Emergent colectomy (44140/44204) |
| L02.211 | Cutaneous abscess of abdominal wall | I&D (10060); document location specifically |
�� Tip: Always Use the 7th Character for Trauma Cases
For injury and trauma diagnoses in general surgery, lacerations, fractures, contusions, foreign bodies — ICD-10-CM requires a 7th character to indicate the encounter type: ‘A’ for initial encounter, ‘D’ for subsequent encounter, and ‘S’ for sequela. Using the wrong 7th character is a common coding error in general surgery emergency cases that results in claim rejection. Train your coders to always confirm the 7th character matches the clinical documentation.
Modifier Most Critical Skill in General Surgery Billing Services
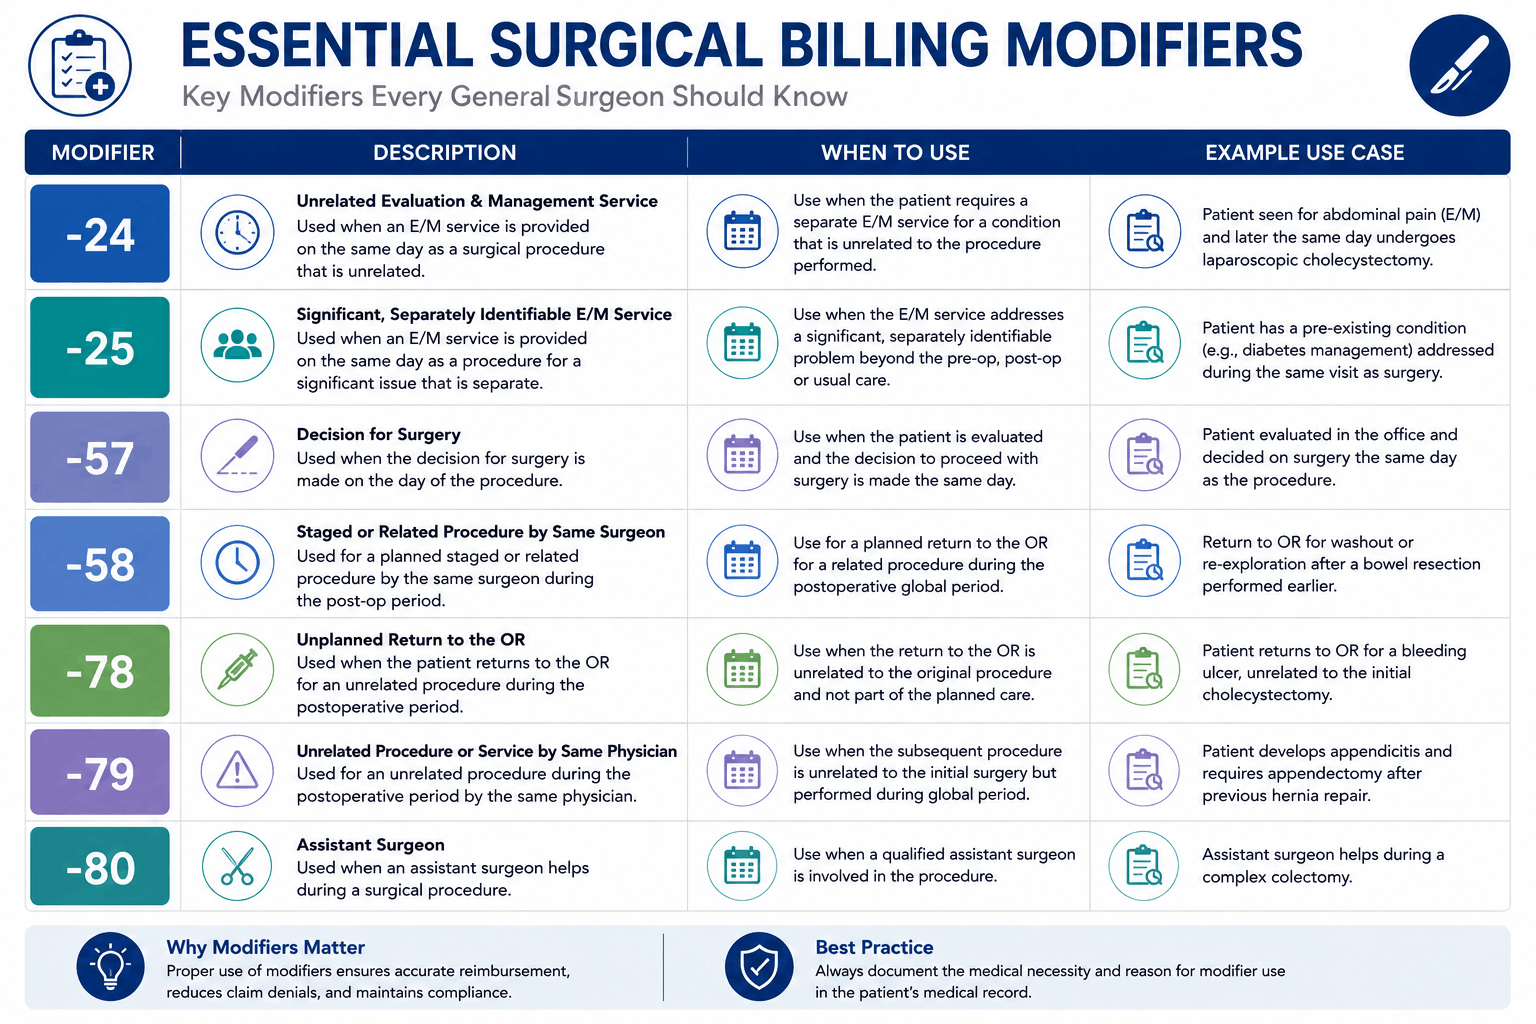
As an experienced surgeon you know that in general surgery billing, modifiers are not optional add-ons, they are essential tools that communicate critical information about the circumstances of every surgical case. Used correctly, they unlock reimbursement for additional services, protect you from global period bundling, and prevent denials.
Complete Modifier Reference for General Surgery Medical Billing
| Modifier | Name | When to Use in General Surgery Billing |
|---|---|---|
| -22 | Increased Procedural Services | Surgery was substantially more complex than typically described by the CPT code. Requires detailed operative note explaining increased complexity. Expect payer to review before paying premium. |
| -23 | Unusual Anesthesia | General anesthesia required for a procedure normally done under local. Document medical necessity for general anesthesia. |
| -24 | Unrelated E/M During Post-Op Period | Office visit during the global period for a condition UNRELATED to the surgery. Document clearly that the issue is unrelated. |
| -25 | Significant, Separately Identifiable E/M | When same-day E/M is separate and significant from the procedure performed. Common in general surgery for decision-to-operate visits. |
| -47 | Anesthesia by Surgeon | Surgeon personally administered regional/general anesthesia — rare, but applicable in some settings. |
| -50 | Bilateral Procedure | Same procedure performed on bilateral anatomical structures in same session. Applies to bilateral hernia repair or bilateral breast procedures. |
| -51 | Multiple Procedures | Second and subsequent procedures in same session, same provider. Primary procedure = no modifier; subsequent procedures get -51. |
| -52 | Reduced Services | Procedure partially performed or reduced at surgeon’s discretion. Document reason clearly in the operative note. |
| -53 | Discontinued Procedure | Procedure started but stopped due to patient safety. More significant than -52; applies when procedure could not be completed. |
| -54 | Surgical Care Only | Surgeon provides surgical care only; post-op care transferred to another physician. |
| -55 | Post-Operative Management Only | Receiving physician provides post-op care only — does not perform surgery. |
| -56 | Pre-Operative Management Only | Rare; surgeon provides only pre-op care, another surgeon performs the operation. |
| -57 | Decision for Surgery | E/M visit at which the decision for major surgery was made, within the global period of another procedure. Prevents bundling of decision visit. |
| -58 | Staged or Related Procedure (Planned) | Return to OR during global period for a planned staged procedure — documented as planned at time of original surgery. |
| -59 | Distinct Procedural Service | Procedures that are normally bundled but are clinically distinct. Use -XS, -XE, -XP, or -XU as more specific alternatives when applicable. |
| -62 | Two Surgeons / Co-Surgeons | Two surgeons of different specialties each perform distinct parts of a surgical procedure. Each bills with -62. |
| -66 | Surgical Team | Complex procedure requiring team of surgeons. Each bills with -66. Requires clear operative documentation of each surgeon’s role. |
| -78 | Return to OR — Related Complication (Unplanned) | Unplanned return to OR during global period for complication of original surgery. |
| -79 | Unrelated Procedure During Global Period | Return to OR during global period for a condition COMPLETELY UNRELATED to the original surgery. |
| -80 | Assistant Surgeon | Another physician assists the primary surgeon. Bill assistant’s charges under -80. |
| -81 | Minimum Surgical Assistant | Minimum assistance provided by a surgeon; less than full assistant role. |
| -82 | Assistant Surgeon — When Qualified Resident Not Available | Applicable in teaching hospital settings when a qualified resident is not available. |
| -AS | PA, NP, CNS as Assistant Surgeon (HCPCS) | Non-physician practitioners assisting in surgery. Different from -80 — used for NPP assistants. |
| -LT / -RT | Left / Right Side | Append to lateralized procedures. Example: right inguinal hernia repair = 49505-RT. |
Laparoscopic vs. Open Surgery Billing — Why Approach Documentation Changes Everything
In general surgery medical billing, the surgical approach is not a minor detail, it is a code-determinative factor. Using the wrong approach code is not a modifier error; it is miscoding that can result in claim denial, incorrect reimbursement, and audit exposure.
Laparoscopic vs. Open: Key Code Pairs in General Surgery Billing
| Procedure | Laparoscopic CPT Code | Open CPT Code |
|---|---|---|
| Cholecystectomy | 47562 | 47600 |
| Appendectomy | 44950 (laparoscopic not always separately coded) | 44950/44960 |
| Colectomy (partial) | 44204 | 44140 |
| Inguinal hernia repair (initial) | 49650 | 49505/49507 |
| Ventral/incisional hernia repair | 49652 | 49560 |
| Nissen fundoplication | 43280 (laparoscopic) | 43327 (open) |
| Splenectomy | 38120 | 38100 |
| Adrenalectomy | 60650 | 60540 |
| Gastric bypass (Roux-en-Y) | 43644 | 43846 |
| Sleeve gastrectomy | 43775 | N/A (typically only laparoscopic) |
Prior Authorization in General Surgery Billing Services
According to our experience the prior authorization (PA) is one of the most important and most time-consuming administrative responsibilities in general surgery billing services. For elective procedures, operating without a valid prior authorization from the payer is virtually guaranteed to result in a zero-payment denial.
Which General Surgery Procedures Typically Require Prior Authorization?
| General Surgery Procedure | Medicare Fee-for-Service | Commercial / Medicare Advantage |
|---|---|---|
| Laparoscopic cholecystectomy (elective) | Generally no PA | Almost always requires PA |
| Emergency cholecystectomy | No PA required | Usually exempt if documented emergency |
| Elective hernia repair | No PA (Medicare FFS) | Commonly requires PA |
| Bowel resection (elective) | No PA (Medicare FFS) | Almost always requires PA |
| Bariatric surgery (sleeve/bypass) | CMS requires clinical criteria | Always requires PA + committee review |
| Thyroid and parathyroid surgery | No PA (Medicare FFS) | Usually requires PA |
| Mastectomy for cancer | No PA (Medicare FFS) | Usually requires PA |
| Breast reconstruction post-mastectomy | No PA (Medicare FFS; WHCRA applies) | Typically requires PA |
| Adrenalectomy | No PA (Medicare FFS) | PA required in most plans |
| Soft tissue tumor excision > 3 cm | No PA (Medicare FFS) | Commonly requires PA |
�� Tip: Get Authorization for the Anticipated Procedure AND Possible Complications
A common problem in general surgery billing: you get PA for a laparoscopic cholecystectomy (47562) but the case converts to open (47600), or you find an unexpected common bile duct stone requiring ERCP. The PA you obtained does not cover these additional procedures. Train your pre-authorization team to request broader authorization language that covers likely related procedures, conversion to open, intraoperative cholangiography (CPT 47563), and possible bile duct exploration. Document all authorization confirmations by number and date in the operative scheduling record.
Medicare and Medicaid Compliance in General Surgery Billing
Medicare and Medicaid are major payers for general surgery practices, particularly for older adult patients presenting with gallbladder disease, hernia, colorectal conditions, and cancer. Each program has specific billing rules that surgical practices must follow.
Medicare-Specific Rules for General Surgery Medical Billing
- Global Surgery Payment Policy: Medicare pays a single fee for surgical services that includes pre-operative, intraoperative, and post-operative care. CMS publishes the global period for every CPT code in the Medicare Physician Fee Schedule. Always verify global periods at: cms.gov/medicare/physician-fee-schedule/search
- Assistant Surgeon Coverage: Medicare covers assistant surgeons (modifier -80) only when the procedure is on the Medicare-approved list of procedures that require an assistant. Use the MPFS lookup tool to verify before billing an assistant surgeon charge to Medicare.
- Teaching Hospital Billing: In academic medical centers, when residents assist or perform portions of surgery, the attending physician must be immediately available and must document participation. Failure to comply with the two-midnight rule and teaching hospital documentation requirements is a high-risk audit area.
- Modifier -22 Policy: Medicare requires an attachment or letter of medical necessity with modifier -22 claims explaining specifically why the procedure was significantly more complex than usual. Without this documentation, Medicare will deny the modifier and pay at the standard rate.
- NCCI Bundling Edits: Medicare’s National Correct Coding Initiative (NCCI) publishes bundling edits that define which procedure code pairs cannot be billed together without a modifier. Always run claims through an NCCI check before submission.
- Women’s Health and Cancer Rights Act (WHCRA): For mastectomy patients, Medicare, and all commercial payers must cover breast reconstruction following a mastectomy for cancer. Ensure your billing team understands reconstruction billing separately from the mastectomy.
Medicaid Considerations for General Surgery Billing
- Medicaid prior authorization requirements are the most burdensome of any payer type — especially for elective general surgery procedures. Build PA workflows specific to each Medicaid managed care organization in your market.
- Medicaid reimbursement rates for surgical procedures are typically 20-40% lower than Medicare rates. Understanding Medicaid payer mix in your practice allows for accurate revenue projections.
- Emergency surgery performed on Medicaid patients typically does not require prior authorization, but must be documented as an emergency in the operative record and on the claim.
- EPSDT (Medicaid for patients under 21) may cover additional surgical services beyond standard Medicaid — verify plan-by-plan for pediatric general surgery patients.
Denial Management for General Surgery Billing
You know that denial management in general surgery billing is not a passive activity, it is an active revenue protection strategy. Every denied claim is recoverable revenue. But only if your team identifies the root cause quickly and appeals within the payer’s filing window.
| Denial Reason | Denial Code | Root Cause in General Surgery | Corrective Action |
|---|---|---|---|
| Missing Prior Authorization | CO-15 | Elective procedure performed without PA or PA number omitted from claim | Implement PA tracking system; include auth number on every elective surgical claim |
| Global Period Bundling | CO-97 | Post-op service billed without correct modifier during global period | Train staff on global periods; apply -24, -58, -78, or -79 modifier as appropriate |
| Wrong Approach Code | CO-11 | Open code billed for laparoscopic procedure (or vice versa) | Implement operative note vs. code audit at charge entry; coder must review op note |
| Medical Necessity Denied | CO-50 | ICD-10 code does not support CPT procedure code | Use most specific ICD-10; link post-op diagnosis to procedure — not pre-op |
| Modifier Missing or Wrong | CO-4 | Bilateral procedure without -50; multiple procedures without -51 | Implement modifier checklist at charge capture; audit claims pre-submission |
| NCCI Bundling Conflict | CO-97 | Two procedures submitted that are bundled per NCCI edits | Run NCCI check before submission; apply -59 or X-modifier with documentation |
| Assistant Surgeon Not Covered | CO-5 | Medicare does not cover assistant surgeon for this procedure | Verify Medicare assistant surgeon approval for CPT code before surgery |
| Timely Filing Exceeded | CO-29 | Claim not submitted within payer’s filing window | Implement claim submission monitoring; submit within 48-72 hours of service |
| Patient Ineligible | CO-27 | Insurance terminated or patient not covered on date of service | Verify eligibility day-of-service for all scheduled surgical cases |
�� Tip: Build a 72-Hour Claim Submission Rule for Surgery
In general surgery billing, every day a claim sits unsubmitted after an operative case is a day you are not getting paid. Implement a firm practice policy: all surgical claims must be coded, scrubbed, and submitted within 72 hours of the procedure.
E/M Billing in General Surgery, Office Visits, Consultations, and Surgical Decision-Making
General surgeons are not only billing for operative procedures in the USA, but they also bill for office-based Evaluation and Management (E/M) services, pre-operative consultations, post-discharge follow-up, and hospital visits. Each has its own billing rules within the context of the global surgical package.
E/M Codes and Global Period Interaction
| E/M Scenario | Modifier Required | Billing Rule |
|---|---|---|
| Office visit — decision for major surgery, same day as surgery | Modifier -57 | Required to unbundle from 90-day global; bill the E/M + -57 |
| Office visit — decision for minor surgery (0/10-day global) | Modifier -25 | Required to bill E/M same day as procedure |
| Post-op visit — unrelated condition during global period | Modifier -24 | Document clearly that condition is unrelated to surgery |
| Hospital visit during global period — unrelated | Modifier -24 | E/M for conditions unrelated to surgery are separately billable |
| Transfer of post-op care | Modifiers -54/-55 | Primary surgeon bills -54; receiving physician bills -55 |
| New patient consult (office) | 99202-99205 | No longer separately payable by Medicare; use standard E/M codes |
| Hospital admission (inpatient initial) | 99221-99223 | Bill when admitting the patient; document MDM level |
| Subsequent hospital visit during global | Included in global package | Do NOT bill separately for routine post-op hospital visits |
Revenue Cycle KPIs for General Surgery Billing Services
Measuring the right metrics is what separates a well-managed general surgery revenue cycle from one that is constantly reactive. These are the KPIs that define high-performing general surgery medical billing services.
| KPI Metric | General Surgery Benchmark | What It Measures |
|---|---|---|
| Clean Claim Rate | > 95% | % of surgical claims accepted without error on first submission |
| Denial Rate | < 5% | % of claims denied; 7-12% without active management in general surgery |
| Days in A/R | < 35 days | Average time from surgery to payment — longer = workflow problem |
| Net Collection Rate | > 96% | % of collectible surgical revenue actually collected |
| A/R > 90 Days | < 10% of total A/R | Aging surgical A/R signals systemic denial or follow-up gaps |
| Claim Submission Lag | < 72 hours | Days between surgery date and claim submission |
| Authorization Denial Rate | < 2% | PA-related denials — should be near zero with proper workflow |
| Modifier Error Rate | < 1% of surgical claims | Modifier errors — tracked via denial CO-4; signals coder training gap |
| Cost to Collect | 5-9% of collections | Total billing cost as % of surgical revenue collected |
| First-Pass Resolution Rate | > 90% | % of denied claims resolved without second-level appeal |
2026 Updates Affecting General Surgery Billing
Keeping up with annual CPT and fee schedule changes is a revenue protection strategy in general surgery. Here is what you need to know for 2026.
2025 Key Updates for General Surgery Medical Billing
- Physician Fee Schedule: The 2025 Medicare PFS continued modest adjustments to RVU values for major surgical procedures. General surgeons should review procedure-specific conversion factor impacts using the CMS MPFS lookup tool.
- E/M Documentation Stability: The 2021 MDM-based E/M documentation rules remain in effect through 2025. Surgeons billing E/M codes alongside operative procedures benefit from the simplified time-based or MDM documentation approach.
- Telehealth for Pre-Op Consultations: CMS extended telehealth flexibility allows some pre-operative consultations to be conducted via telehealth with modifier -95, reducing patient burden for elective surgery scheduling.
- NCCI Edit Updates: CMS updates NCCI edits quarterly. Surgical billing teams must review quarterly NCCI updates to identify any new bundling restrictions affecting high-volume procedure code pairs.
Upcoming 2026 Changes to Watch
- CPT Code Revisions in Surgery Range: The AMA’s 2026 CPT update introduces revisions to several surgical code families. Review the 2026 CPT Manual or AMA release notes for changes in the 40000-49999 (GI/abdominal) and 60000-60699 (endocrine) surgery code ranges.
- Reimbursement Pressure: CMS has projected a 2.93% conversion factor reduction in the 2026 PFS. For high-volume surgical practices, this reduction in RVU conversion values should be modeled against current procedure volume to assess revenue impact.
- Robotic Surgery Billing Clarifications: As robotic-assisted surgery becomes more common in general surgery (robotic cholecystectomy, robotic hernia repair), expect continued payer guidance clarifying how robotic-assisted procedures should be coded. Currently, robotic-assisted procedures use the same laparoscopic CPT codes — but always verify with your payer.
- Prior Authorization Transparency: CMS has implemented new PA transparency rules requiring Medicare Advantage plans to publish their PA requirements. This helps surgical practices build more accurate PA workflows for MA patients.
Frequently Asked Questions: General Surgery Billing Services
What is included in the global surgical package?
The global surgical package includes the pre-operative evaluation on the day of surgery (and one day before for major procedures), the intraoperative services, all routine post-operative care within the global period, and complications that do not require a return to the OR. Separate services, unrelated conditions, return-to-OR complications, diagnostic tests, and staged procedures — can be billed separately with the correct modifier.
What modifiers are needed when billing post-op services during the global period?
Use modifier -24 for unrelated E/M services during the global period; -58 for planned staged procedures returning to the OR; -78 for unplanned returns to the OR for complications related to the original surgery; and -79 for unrelated procedures performed during the global period. Using the wrong modifier or no modifier results in bundling denials.
How do I bill when a laparoscopic procedure converts to open?
Bill only the open procedure code (since that is what was ultimately performed). Do not bill both the laparoscopic and open codes. Document the conversion clearly in the operative note and consider modifier -22 (Increased Procedural Services) if the conversion significantly increased complexity and operative time, with full supporting documentation attached.
Does House of Outsourcing handle billing for both professional and facility surgical charges?
Yes. House of Outsourcing provides general surgery billing services for professional (physician) charges, and our team works with facility billing teams to coordinate claims for ambulatory surgery center (ASC) and hospital outpatient department (HOPD) encounters. Contact us to discuss your specific practice structure and billing needs at www.houseofoutsourcing.com.
Related Billing and Revenue Cycle Guides
- General Surgery RCM Guidelines for Better Collections
- Physical Therapy Billing: Minutes, Modifiers & Documentation
Need support with your billing workflow? Explore our medical billing and revenue cycle services or request a free consultation.
Medical Billing Services @ 2.45% of Total Collection
Get a free assessment from our billing experts
