


Emergency Medicine RCM guidelines provide healthcare organizations with a structured approach to managing complex emergency billing workflows, improving coding accuracy, reducing claim denials, and optimizing reimbursement. Effective RCM practices help emergency departments maintain compliance, streamline revenue operations, and ensure financial stability in a fast-paced care environment.

The Complete 2026 Guide to Emergency Medicine Medical Billing Services for US Emergency Practices
Emergency medicine is the front door of American healthcare. Every hour of every day, regardless of insurance status, time of day, or presenting condition, emergency departments absorb the full spectrum of human medical need. And every single one of those encounters generates a billing claim that must be coded accurately, submitted on time, documented to government and commercial payer standards, and collected from some combination of Medicare, Medicaid, commercial insurance, workers’ compensation, or a self-pay patient.
According to the Centers for Disease Control and Prevention (CDC), US emergency departments handle approximately 145 million visits annually. That represents an extraordinary volume of billing activity,, and an equally extraordinary volume of revenue risk when claims aren’t coded correctly, documented completely, or managed proactively through the denial cycle.
Our this complete and accurate guide gives emergency medicine practitioners, billing professionals, and hospital administrators a complete, practical framework for emergency medicine medical billing, from E/M level selection and critical care coding to procedure billing, EMTALA compliance, payer-specific rules, and the revenue cycle strategies that separate high-performing EDs from chronically underpaid ones.
Related Billing and Revenue Cycle Guides
Need support with your billing workflow? Explore our medical billing and revenue cycle services or request a free consultation.
Table of Contents
- What Is Emergency Medicine Medical Billing?
- What Makes Emergency Medicine Medical Billing Services Uniquely Challenging
- Emergency Department E/M Levels: CPT 99281–99285 Explained
- Critical Care Billing in Emergency Medicine Medical Billing Services
- ED Procedure CPT Codes: Laceration Repair, Fracture Care, and More
- Imaging and Diagnostic Billing in Emergency Medicine Medical Billing
- Observation vs. Inpatient Admission Billing in Emergency Medicine Medical Billing Services
- Facility vs. Professional Billing in Emergency Medicine Medical Billing
- ICD-10 Diagnosis Coding for Emergency Medicine Medical Billing Services
- Modifiers That Protect Emergency Medicine Claims
- Medicare and Medicaid Rules for Emergency Medicine Medical Billing Services
- EMTALA: The Legal Foundation of Emergency Medicine Billing Compliance
- Documentation Requirements for Emergency Medicine Medical Billing Services
- Charge Capture in Emergency Medicine Medical Billing
- Common Denial Reasons in Emergency Medicine Medical Billing Services
- Compliance and Audit Risks in Emergency Medicine Medical Billing
- Revenue Cycle KPIs for Emergency Medicine Medical Billing Services
- How House of Outsourcing Elevates Your Emergency Medicine Medical Billing Services
What is Emergency Medicine Medical Billing?
Emergency medicine medical billing is the process of accurately coding, submitting, and collecting payment for all clinical services delivered in hospital emergency departments including evaluation and management visits, critical care, diagnostic procedures, imaging interpretation, laceration repairs, fracture management, airway procedures, and a wide range of other acute interventions.
Unlike most outpatient specialties, emergency medicine medical billing operates under a unique set of constraints:
- No scheduled encounters,It means that every patient arrives unpredictably
- No prior authorization, possible before acute care is delivered
- Dual billing streams, professional (physician) and facility (hospital) claims for the same encounter
- Mandatory care regardless of insurance, EMTALA requires stabilizing treatment regardless of ability to pay
- High payer mix complexity, Medicare, Medicaid, commercial, workers’ comp, auto liability, and self-pay all coexist
- No new vs. established patient distinction, ED E/M codes apply to all patients equally
- Time is not a billing driver, unlike most E/M settings, ED level selection is based on Medical Decision Making, not time
What Makes Your Emergency Medicine Practice Billing Uniquely Challenging
Here we will try our best to name the specific challenges that make your emergency medicine medical billing harder than most other specialties, because understanding the problem is the first step to solving it. Here are the main six points you need to understand to make your practice billing process smooth and accurate.
Documentation Under Fire
According to our experience emergency physicians are simultaneously treating multiple patients in a high-acuity environment. Documentation happens in real time, under pressure, often using dictation or EHR templates that don’t always capture the clinical complexity that actually occurred. Incomplete documentation = lower-level billing = lost revenue.
The Dual-Claim Reality
Every ED encounter generates two separate claims, one from the facility (hospital) and one from the physician group. These claims use different claim forms (UB-04 vs. CMS-1500), different codes, and different reimbursement logic. Misalignment between facility and professional billing creates compliance exposure.
Payer Mix Volatility
On a typical ED shift, the payer mix might include Medicare, Medicaid, four different commercial insurers, workers’ compensation, and a third of patients with no insurance at all. Each payer has its own rules. Managing that complexity requires systems,not guesswork.
Charge Capture Leakage
In the clinical chaos of a busy ED, procedures get performed but not documented, medications get administered but not captured, and supply charges slip through without a billing code. Every missed charge is revenue that walks out the door permanently.
Observation vs. Inpatient Status Decisions
The decision to admit a patient as inpatient vs. place them in observation status has enormous financial implications, for the hospital, for the physician, and for the patient. Getting it wrong creates compliance exposure and payment discrepancies that are difficult to fix after the fact.
High Denial Rates
Emergency medicine consistently sees some of the highest claim denial rates in US healthcare, driven by medical necessity disputes, E/M level disagreements, and the “surprise billing” regulatory environment created by the No Surprises Act.
Emergency Department E/M Levels: CPT 99281–99285 Explained
The five ED E/M codes (99281–99285) are the foundation of emergency medicine medical billing. Unlike outpatient E/M codes, these codes apply to all patients, new and established, and are selected exclusively based on Medical Decision Making (MDM). Time is explicitly excluded as a basis for ED E/M level selection per the American Medical Association (AMA).
The Five ED E/M Levels — Professional Charges
| CPT Code | MDM Level | Typical Presenting Problems | Clinical Examples |
|---|---|---|---|
| 99281 | Straightforward | Self-limited; may not require physician presence | Insect bite (uncomplicated), wound check, routine BP check, TB test read |
| 99282 | Low complexity | Self-limited or minor; OTC treatment; simple decisions | URI, minor abrasion, earache, mild allergic reaction without systemic involvement |
| 99283 | Moderate complexity | Multiple presenting problems; some treatment decision complexity | Ankle sprain with imaging, moderate asthma exacerbation, UTI with comorbidities |
| 99284 | Moderate-high complexity | New problem requiring workup; prescription drug management | Chest pain requiring ECG and labs, abdominal pain with imaging, hypertensive urgency |
| 99285 | High complexity | Severe presenting problems; high risk of morbidity/mortality | STEMI, sepsis, stroke, polytrauma, respiratory failure, DKA with complications |
💡 Tip #1: Train ED Physicians to Document MDM Explicitly, Not Implicitly. The single most common source of revenue loss in your emergency medicine medical billing is the inability to justify 99285 billing because the documentation describes what the physician did but not why the decision-making was complex. So you need to explicitly document the number of problems assessed, the tests ordered and why, the differential diagnoses considered, and the risk level of the management plan chosen.
Critical Care Billing in Emergency Medicine Medical Billing Services
Critical care billing is one of the highest-value and most audited areas in emergency medicine medical billing services. When you provide critical care services, the billing shifts from the ED E/M codes (99281–99285) to the critical care time-based codes.
Critical Care CPT Codes
| CPT Code | Description | Requirements |
|---|---|---|
| 99291 | Critical care — first 30–74 minutes | Physician personally manages critically ill or injured patient; time-based |
| 99292 | Critical care — each additional 30 minutes | Add-on to 99291; document total accumulated time |
What’s Included in Critical Care Time (Cannot Be Billed Separately)
The following services are included in your medical practice critical care billing and cannot be billed separately when performed during the critical care encounter:
- Interpretation of cardiac output measurements
- Chest X-ray interpretation (if performed by the treating physician)
- Pulse oximetry
- Blood gases interpretation
- Peripheral blood smear review
- Temporary transcutaneous pacing
- Ventilator management
- Vascular access procedures (venipuncture, IV placement)
What Can Be Billed Separately Alongside Critical Care
| CPT Code | Service | Notes |
|---|---|---|
| 31500 | Endotracheal intubation | Separately billable with critical care |
| 36556 | Central venous catheter placement | Separately billable |
| 36620 | Arterial line insertion | Separately billable |
| 32551 | Tube thoracostomy (chest tube) | Separately billable |
| 92950 | Cardiopulmonary resuscitation (CPR) | Separately billable |
| 99466–99467 | Critical care transport, pediatric | When applicable |
💡 Tip #2: Document Critical Care Time Precisely — Start Time, Stop Time, Total Minutes. CMS requires your medical practice to document the total time spent on critical care services. Without documented time, the critical care code cannot be supported. Your documentation must also clarify that the time was spent in direct management of the critically ill patient, not in incidental proximity.
ED Procedure CPT Codes: Laceration Repair, Fracture Care, and More

Procedures performed in the emergency department of your medical practice generate significant additional revenue beyond the E/M visit. Capturing these codes correctly is essential to complete emergency medicine medical billing services.
Laceration Repair CPT Codes
| CPT Code | Type | Location | Size |
|---|---|---|---|
| 12001 | Simple repair | Scalp, neck, axilla, external genitalia, trunk, extremities | 2.5 cm or less |
| 12002 | Simple repair | Same locations | 2.6–7.5 cm |
| 12004 | Simple repair | Same locations | 7.6–12.5 cm |
| 12011 | Simple repair | Face, ears, eyelids, nose, lips, mucous membranes | 2.5 cm or less |
| 12013 | Simple repair | Face/ears/nose/lips | 2.6–5.0 cm |
| 12031 | Intermediate repair | Scalp, axilla, trunk, extremities | 2.5 cm or less |
| 12032 | Intermediate repair | Same | 2.6–7.5 cm |
| 12034 | Intermediate repair | Same | 7.6–12.5 cm |
| 12041 | Intermediate repair | Neck, hands, feet, genitalia | 2.5 cm or less |
| 12051 | Intermediate repair | Face/ears/nose/lips | 2.5 cm or less |
| 13100 | Complex repair | Trunk | 1.1–2.5 cm |
| 13120 | Complex repair | Scalp, arms, legs | 1.1–2.5 cm |
| 13131 | Complex repair | Forehead, cheeks, chin, ears, eyelids, nose, lips | 1.1–2.5 cm |
Fracture and Dislocation CPT Codes
| CPT Code | Service |
|---|---|
| 25600 | Closed treatment of distal radius fracture — without manipulation |
| 25605 | Closed treatment of distal radius fracture — with manipulation |
| 27750 | Closed treatment of tibial shaft fracture — without manipulation |
| 27752 | Closed treatment of tibial shaft fracture — with manipulation |
| 27810 | Closed treatment of ankle fracture — without manipulation |
| 27816 | Closed treatment of ankle fracture — with manipulation |
| 23600 | Closed treatment of proximal humeral fracture — without manipulation |
| 26600 | Closed treatment of metacarpal fracture — without manipulation |
| 28490 | Closed treatment of great toe fracture — without manipulation |
💡 Tip #3: Never Let Procedure Codes Walk Out the Door With the Patient. In a busy ED, it is entirely common for your emergency practice to suture a laceration, splint a fracture, perform an I&D, AND interpret an ECG all in one patient encounter, and have the billing team only capture the E/M code. Procedure codes are separate, additional reimbursement, and they require separate documentation (procedure note). Build a procedure charge capture checklist into your ED charge entry workflow so that every billable procedure is captured before the patient is discharged.
Imaging and Diagnostic Billing in Emergency Medicine Medical Billing Services
Imaging interpretation is a significant revenue component in emergency medicine medical billing, particularly when emergency physicians perform real-time interpretation of X-rays, CT scans, or ultrasounds during the acute evaluation.
ED Imaging Interpretation CPT Codes
| CPT Code | Service | Notes |
|---|---|---|
| 71046 | Chest X-ray — 2 views | Most common ED chest imaging |
| 71045 | Chest X-ray — 1 view | Single frontal or lateral |
| 72198 | MRI pelvis without/with contrast | ED pelvic pain workup |
| 73610 | X-ray ankle — minimum 3 views | Trauma imaging |
| 73630 | X-ray foot — minimum 3 views | Foot trauma |
| 73100 | X-ray wrist — 2 views | |
| 76705 | Ultrasound, abdominal, limited | FAST exam component |
| 76857 | Ultrasound, pelvic, limited | ED pelvic pain evaluation |
| 76942 | Ultrasound guidance for needle placement | ED procedures with US guidance |
Observation vs. Inpatient Admission Billing in Emergency Medicine Medical Billing Services
One of the most consequential and most misunderstood, decisions in emergency medicine medical billing is the determination of whether a patient should be placed in observation status or admitted as an inpatient. This decision has massive implications for payment, patient financial responsibility, and compliance.
Observation vs. Inpatient: The Key Distinctions
| Factor | Observation Status | Inpatient Admission |
|---|---|---|
| Typical duration | Hours to <24 hrs (can extend to 48 hrs) | Expected ≥2 midnight stays |
| Medicare billing basis | Outpatient (Part B) | Inpatient (Part A) |
| Patient cost-sharing | May owe more (Part B cost-sharing applies) | Typically Part A deductible |
| Criteria | Expected to resolve in <2 midnights | Physician judgment + expected ≥2 midnight stay |
| Clinical documentation need | Medical necessity for monitoring; documented improvement expected | Medical necessity for inpatient level of care; ≥2 midnight expectation documented |
Facility vs. Professional Billing in Emergency Medicine Medical Billing Services
According to our decade of experience we know that emergency medicine medical billing is unique because every single ED encounter generates TWO separate claims, one from the hospital facility and one from the physician (or physician group). These claims are submitted separately, coded differently, and reimbursed through different mechanisms.
Understanding the Two Billing Streams
| Element | Facility Claim (Hospital) | Professional Claim (Physician) |
|---|---|---|
| Claim form | UB-04 | CMS-1500 |
| Revenue codes | 0450 (Emergency Room) | N/A |
| E/M codes | Same 99281–99285 but based on facility resources | Same 99281–99285 based on physician MDM |
| What’s captured | Nursing, supplies, equipment, facility overhead, ancillary services | Physician cognitive work and procedures performed by physician |
| Who bills | Hospital billing department | Physician group or independent billing company |
| Place of service | 23 (ED) | 23 (ED) |
| Reimbursement basis | APC (Ambulatory Payment Classification) under OPPS for Medicare | RBRVS (RVU-based) physician fee schedule |
ICD-10 Diagnosis Coding for Emergency Medicine Medical Billing
ICD-10 coding in emergency medicine medical billing is driven by the presenting problem and the working or confirmed diagnosis at the time of ED disposition. The coder’s job is to capture the most accurate, specific diagnosis that reflects the clinical picture at discharge.
Most Common ED ICD-10 Diagnosis Categories
| ICD-10 Code Range | Condition Category | High-Volume ED Codes |
|---|---|---|
| R07.9 | Chest pain, unspecified | Always try to specify type |
| R07.1 | Chest pain on breathing | Pleuritic chest pain |
| I21.9 | STEMI, unspecified | ACS presentations |
| I21.4 | NSTEMI | Troponin-positive ACS |
| R55 | Syncope and collapse | Common undifferentiated presentation |
| I63.9 | Cerebral infarction, unspecified | Acute stroke |
| I61.9 | Nontraumatic intracerebral hemorrhage | Hemorrhagic stroke |
| J18.9 | Pneumonia, unspecified | Community-acquired pneumonia |
| J80 | Acute respiratory distress syndrome | High-acuity respiratory failure |
| J96.00 | Acute respiratory failure, unspecified | — |
| A41.9 | Sepsis, unspecified | Code the causative organism when known |
| A41.01 | Sepsis due to MRSA | Organism-specific sepsis |
| S06.0X0A | Concussion — initial encounter | Traumatic brain injury |
| S72.001A | Fracture of unspecified part of neck of femur — initial | Hip fracture |
| S52.501A | Fracture of lower end of radius — initial | Distal radius fracture |
| T14.91XA | Suicide attempt — initial encounter | Behavioral emergency |
| R41.3 | Other amnesia | Altered mental status workup |
| N10 | Acute pyelonephritis | Urinary tract infection with systemic features |
| K35.80 | Acute appendicitis — without abscess | Surgical abdomen |
| K92.1 | Melena | GI bleeding |
| K92.0 | Hematemesis | Upper GI bleeding |
| K57.30 | Diverticulosis of large intestine — without perforation | — |
| G43.909 | Migraine, unspecified | Headache presentations |
| R51.9 | Headache, unspecified | When migraine not confirmed |
| T36.0X1A | Poisoning by penicillins, accidental — initial | Overdose/poisoning presentations |
| T50.901A | Poisoning by unspecified drug — accidental | General overdose coding |
💡 Tip #4: Code the Definitive Diagnosis When Available at Discharge, Not Just the Presenting Symptom. A common undercoding pattern in emergency medicine medical billing is coding the presenting symptom (chest pain R07.9) when the physician has actually documented a working or confirmed diagnosis (unstable angina I20.0) at the time of disposition. ICD-10 coding guidelines allow and encourage coding the confirmed or most specific diagnosis available at discharge. Symptom codes (R codes) should only be used when no definitive diagnosis has been established.
Modifiers That Protect Your Practice Emergency Medicine Claims
Modifiers in emergency medicine medical billing communicate critical context to payers. Missing or misapplied modifiers are one of the fastest paths to denial in the ED billing environment.
Essential Modifiers in Emergency Medicine Medical Billing
| Modifier | Name | ED Application |
|---|---|---|
| 25 | Separate E/M Service | E/M billed same day as a procedure (e.g., 99284 + laceration repair) |
| 59 | Distinct Procedural Service | Two procedures not normally billed together; separate anatomical sites or sessions |
| XS | Separate Structure | Preferred alternative to -59 for separate anatomical site |
| 76 | Repeat Procedure Same Physician | Same procedure repeated same day (e.g., second I&D of different abscess) |
| 27 | Multiple Outpatient Hospital E/M Encounters on Same Date | Patient seen multiple times in ED same day |
| GJ | “Opt-Out” Physician or Practitioner | Non-participating provider disclosure |
| CR | Catastrophe/Disaster Related | Disaster-related emergency services |
| NU | New Equipment | For new durable medical equipment supplied in ED |
| KX | Medicare LCD Requirements Met | Documents coverage criteria satisfied for specific service |
| 50 | Bilateral Procedure | Bilateral procedures performed in same session |
| 52 | Reduced Services | Procedure partially performed |
| 53 | Discontinued Procedure | Procedure started but discontinued for patient safety reason |
Medicare and Medicaid Rules for Emergency Medicine Medical Billing
Medicare and Medicaid together account for a significant portion of most emergency departments’ payer mix, and both have specific rules that emergency medicine billing teams must master.
Medicare ED Billing Rules
- ED E/M codes 99281–99285 are covered for Medicare patients when medically necessary
- Level selection must be supported by MDM documentation
- Critical care (99291–99292) is covered when patient meets the critical illness/injury definition
- Medicare does NOT differentiate between new and established patients for ED E/M codes
- The Emergency Medical Treatment and Labor Act (EMTALA) requires that Medicare-participating EDs provide screening and stabilizing care regardless of ability to pay or insurance status
- The No Surprises Act (effective 2022) limits out-of-network billing for ED services — physician groups must comply with these protections for insured patients
| Medicare ED Coverage | Covered | Key Requirement |
|---|---|---|
| ED E/M (99281–99285) | Yes | MDM documentation supports level |
| Critical care (99291/99292) | Yes | Time documented; patient meets critical criteria |
| Laceration repair | Yes | Technique documented |
| Fracture care | Yes | Type and manipulation status documented |
| Endotracheal intubation (31500) | Yes | Procedure note required |
| Central line placement (36556) | Yes | Separate from critical care unless non-emergent |
| ECG interpretation (93010) | Yes | Only if ED physician provides the interpretation |
| Chest X-ray interpretation (71046-26) | Yes | Only if no radiologist interpretation available |
The Legal Foundation of Emergency Medicine Billing Compliance
The Emergency Medical Treatment and Labor Act (EMTALA) is the federal law that requires Medicare-participating hospitals to provide a medical screening examination and stabilizing treatment to any person who presents to the emergency department, regardless of their ability to pay, insurance status, or citizenship.
EMTALA doesn’t directly govern billing, but it creates the clinical mandate that underlies all emergency medicine billing compliance. You cannot refuse to see a patient. You cannot delay a medical screening examination based on billing or insurance concerns. And you cannot discharge an unstable patient for financial reasons.
| EMTALA Requirement | Billing Implication |
|---|---|
| Mandatory medical screening examination | Must be documented regardless of whether patient can pay |
| Stabilizing treatment required | All services rendered must be documented for potential billing |
| No delay for insurance verification | Pre-registration is permitted; actual care cannot wait on insurance confirmation |
| Transfer requirements if unstable | Transfer documentation must support medical necessity |
| On-call physician requirements | On-call specialist billing must reflect actual services rendered |
Documentation Requirements for Emergency Medicine Medical Billing Services
In emergency medicine, documentation is the clinical record and the billing justification simultaneously. There is no room to retroactively upgrade documentation to support a higher bill. The note must reflect what actually happened, and what actually happened must be documented thoroughly enough to support the E/M level billed.
The Eight Must-Have Documentation Elements for Every ED Encounter
| Documentation Element | Required | ED-Specific Notes |
|---|---|---|
| Chief complaint | Yes | Patient’s presenting symptom in their own words when possible |
| History of Present Illness (HPI) | Yes | Onset, duration, severity, location, modifying factors, associated symptoms |
| Review of Systems (ROS) | For higher levels | Relevant systems; pertinent positives AND negatives documented |
| Physical examination | Yes | All relevant systems examined; findings documented specifically |
| Diagnostic test results | Yes | Ordered tests AND their results, with interpretation |
| Medical decision-making | Yes | Problems assessed, data reviewed, risk of management options |
| Procedures performed | When applicable | Separate procedure note with technique, findings, closure method |
| Disposition | Yes | Admission, discharge, transfer, or observation — with documented rationale |
What is Charge Capture in Emergency Medicine Medical Billing?
As an experienced physician you know that charge capture is the process of identifying and recording every billable service provided during an ED encounter before the patient leaves your medical practice. In emergency medicine, charge capture is consistently one of the biggest sources of revenue leakage across the nation.
Common Charge Capture Failures in Emergency Medicine Medical Billing
| Missed Service | Why It’s Frequently Missed | Revenue Impact |
|---|---|---|
| Laceration repair CPT code | Physician documents the repair but doesn’t enter a procedure charge | Entire procedure revenue lost |
| Splinting | Applied by nursing but no procedure code entered | Lost ancillary revenue |
| I&D of abscess | Included in E/M note but not charged separately | Lost procedure revenue |
| ECG interpretation | Tracing done, result documented, but 93010 never charged | Lost interpretation fee |
| Critical care | Patient clearly critically ill but 99285 billed instead of 99291/99292 | Significant revenue gap |
| Second procedure at different site | First procedure captured, second missed | Partial revenue capture |
| IV catheter placement | Nursing places IV; charge not captured | Small but cumulative loss |
| Nebulizer treatments | Administered but not charged | Per-treatment loss |
💡 Tip #5: Implement a Real-Time Charge Capture Checklist as Part of the Discharge Workflow. Build a mandatory charge capture checkpoint into the discharge process, a brief review of the patient’s encounter that asks: Was a procedure performed? Was critical care provided? Was an ECG interpreted? Was a splint applied? This takes 60 seconds and recovers charges that would otherwise be permanently lost. Electronic charge capture tools integrated with your EHR can automate much of this process.
What Are Common Denial Reasons in Emergency Medicine Medical Billing?
According to our two decades of billing experience, denials in emergency medicine are both predictable and preventable. Here’s the complete landscape of why ED claims get denied, and exactly what to do about each one.
| Denial Reason | Root Cause | Prevention Strategy |
|---|---|---|
| E/M level downcoded by payer | Documentation doesn’t explicitly support MDM complexity | MDM documentation training; separate clinical rationale from plan |
| Medical necessity denial on 99285 | Payer algorithm flags high-level visit without documented high-risk condition | Explicit MDM documentation with risk elements stated |
| Missing modifier -25 | E/M and procedure submitted same day without -25 on E/M | Build modifier -25 into all procedure encounters in claim scrubber |
| Critical care not supported | 99291 billed but time not documented or patient doesn’t meet criteria | Document time explicitly; define critical illness in note |
| Observation vs. inpatient status dispute | Inpatient admission without 2-midnight documentation | Admission note must include expected stay duration and medical reason |
| Untimely filing | Claim submitted after payer deadline | Monitor filing windows; automate submission workflows |
| Eligibility/coverage lapsed | Patient’s insurance not active at time of service | Real-time eligibility check at registration; Medicaid retro-eligibility search |
| No Surprises Act dispute | Out-of-network billing for ED services | Comply with NSA; use IDR for payment disputes |
| Duplicate claim | Same encounter billed twice | Claim scrubber deduplication check |
| Procedure bundled into E/M | Laceration repair or I&D denied as included in E/M | Apply modifier -25 to E/M; procedure note clearly separate |
| Missing procedure documentation | Procedure code billed but no procedure note in record | Mandatory procedure note for every procedure code billed |
| Wrong place of service code | POS 23 not used for ED professional claims | Automate POS code verification in billing workflow |
| ICD-10 code mismatch | Diagnosis doesn’t support the procedure billed | Coding review to ensure procedure-diagnosis alignment |
| Workers’ comp missing injury documentation | WC claim without documentation of workplace injury | Injury documentation required in clinical note |
Why Compliance and Audit Risks in Emergency Medicine Medical Billing is Higher?
You know that emergency medicine is a high-priority audit target for both CMS and commercial payers. The combination of high visit volume, high E/M levels, and the 99285/critical care billing profile makes ED billing a consistent focus of Recovery Audit Contractor (RAC) reviews and commercial payer audits.
Top OIG and CMS Audit Targets in Emergency Medicine
- E/M upcoding: Billing 99285 without documented high-complexity MDM
- Critical care time misrepresentation: Billing 99291 without documented time or patient meeting critical care criteria
- Unbundling procedures from E/M: Billing procedure codes that are included in the E/M without separate documentation
- Observation billing compliance: Inpatient admissions without 2-midnight documentation
- Duplicate billing: Facility and professional teams billing for the same physician services
Building an Emergency Medicine Compliance Program
A functional compliance framework for emergency medicine medical billing services includes:
Monthly chart audits: Random sample of 20–30 encounters per provider; focus on 99285 and critical care levels; compare documentation to billed level
Denial trend analysis: Weekly review of denial patterns by reason code; identify systemic issues vs. individual errors
E/M level distribution monitoring: Track the distribution of 99281–99285 across providers; significant outliers (e.g., one physician billing 99285 90% of the time) warrant review
No Surprises Act compliance audits: Quarterly review of out-of-network billing practices and IDR submissions
EMTALA documentation review: Annual audit of medical screening examination documentation and transfer log compliance
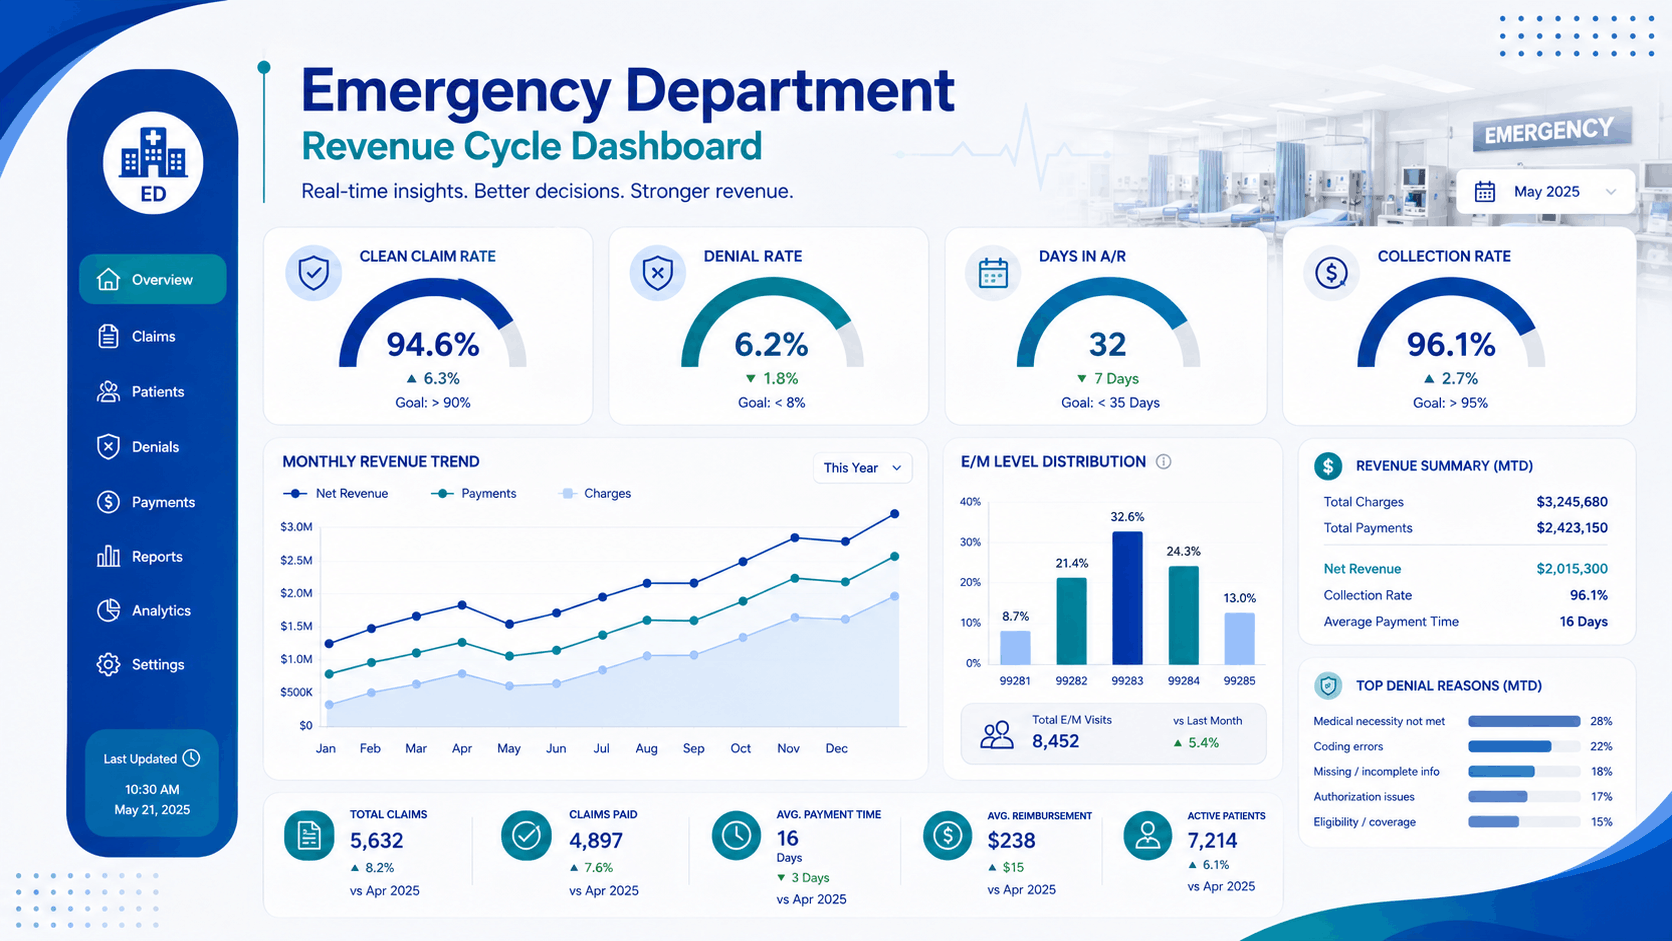
What Are Revenue Cycle KPIs for Emergency Medicine Medical Billing
Measuring the right performance indicators tells you exactly where your emergency medicine medical billing are working, and where they’re bleeding.
| KPI | Benchmark Target | Emergency Medicine Context |
|---|---|---|
| Clean Claim Rate | ≥ 95% | High-volume ED requires automated scrubbing |
| Days in AR | < 35 days | ED has complex payer mix; longer than typical outpatient |
| Denial Rate | < 10% | Industry ED average is 15–25%; <10% is high-performing |
| First Pass Acceptance Rate | ≥ 90% | Each denied claim costs 2–3x the original submission cost to work |
| Collection Rate | ≥ 95% of net collectibles | High self-pay portion makes patient collections critical |
| Appeal Success Rate | ≥ 65% | ED denials are often documentation-fixable |
| 99285 Utilization Rate | Reviewed quarterly | Should match acuity profile of patient population |
| Critical Care Utilization Rate | Tracked vs. ICU admission rate | Should correlate; outliers warrant review |
| Self-Pay Collection Rate | ≥ 30% | Emergency self-pay is the hardest collection in medicine |
| Charge Capture Rate | ≥ 98% of services rendered | Real-time charge entry reduces leakage |
| Coding Accuracy Rate | ≥ 97% | High volume amplifies impact of individual code errors |
The Full Emergency Medicine Revenue Cycle
| Phase | Key Activities | Emergency Medicine-Specific Considerations |
|---|---|---|
| Patient Arrival | Registration, ID verification, payer identification | Eligibility check in real time; self-pay flagged for financial counseling |
| Clinical Care | Physician evaluation, procedures, disposition | All services documented simultaneously with care delivery |
| Charge Entry | Real-time charge capture, procedure codes, critical care time | Checklist-based; before patient disposition |
| Coding | E/M level selection, ICD-10, modifier assignment | MDM-based level selection; definitive diagnosis when available |
| Claim Submission | Dual streams (facility + professional), scrubbing, timely filing | Both claim types submitted within payer windows |
| Payment Posting | ERA reconciliation, underpayment identification | No Surprises Act payment compliance monitored |
| Denial Management | E/M level appeals, medical necessity appeals | Clinical documentation retrieved; physician available for peer-to-peer |
| Patient Collections | Self-pay balances, charity care, payment plans | Financial counseling at point of service for high self-pay proportion |
| Retroactive Eligibility | Medicaid presumptive eligibility verification | Self-pay patients checked for retroactive Medicaid coverage |
| Analytics | E/M distribution, denial trending, charge capture audit | Monthly reports to ED medical director and practice manager |
Frequently Asked Questions (FAQs) About Emergency Medicine Medical Billing Services
Why can’t emergency medicine use time to determine E/M level?
The AMA specifically excludes time as a basis for ED E/M level selection because emergency physicians commonly manage multiple patients simultaneously during a shift, making it impractical to assign time exclusively to any single patient. Instead, ED E/M levels are driven entirely by Medical Decision Making complexity.
Can we bill 99285 (Level 5) and critical care (99291) for the same patient encounter?
No. Critical care (99291/99292) and ED E/M codes (99281–99285) are mutually exclusive on the same day for the same patient by the same physician. When critical care is provided, bill 99291/99292 instead of the ED E/M code. However, certain procedures (intubation, central line) may be billed separately alongside critical care.
What is the No Surprises Act and how does it affect our ED billing?
The No Surprises Act (effective January 2022) prohibits out-of-network emergency physicians from balance-billing patients beyond in-network cost-sharing amounts. If your physician group is out-of-network at a hospital, you must accept payment based on the qualifying payment amount from the insurer, not your billed charges. Payment disputes go through the Independent Dispute Resolution (IDR) process.
Can your practice bill for both the facility and the physician separately for the same ED encounter?
Yes. The facility (hospital) and the physician (or physician group) submit separate claims for the same encounter. This is standard practice in emergency medicine, facility claims use UB-04 and capture hospital resources; professional claims use CMS-1500 and capture physician cognitive work and physician-performed procedures. This is not double-billing.
Medical Billing Services @ 2.45% of Total Collection
Get a free assessment from our billing experts
