
Our Pediatrics Medical Billing services help practices navigate complex pediatric coding requirements, insurance guidelines, and evolving reimbursement challenges. We manage the complete billing cycle—from accurate claim submission and eligibility verification to denial resolution and A/R follow-up—to improve reimbursements, reduce administrative workload, and support healthy practice growth.

This guide is built for US pediatricians, practice managers, and healthcare administrators who want a definitive resource on pediatrics medical billing services:
| # | Section Title | Page Focus |
|---|---|---|
| 1 | What Is Pediatrics Medical Billing? | Overview & unique challenges |
| 2 | Why Pediatrics Billing Requires Specialized Expertise | Complexity factors |
| 3 | Key CPT Codes in Pediatrics Medical Billing | Well-child, sick visits, immunizations |
| 4 | Pediatrics Medical Billing Services: Full Scope | End-to-end service breakdown |
| 5 | ICD-10 Coding in Pediatrics Billing | Diagnosis codes by age group |
| 6 | Medicaid & CHIP Billing Rules for Pediatricians | Government payer guidelines |
| 7 | Preventive Care & Well-Child Visit Billing | EPSDT, AAP schedule billing |
| 8 | Immunization Billing in Pediatric Medical Billing Services | VFC, administration codes |
| 9 | Common Pediatrics Billing Denials & How to Fix Them | Denial management |
| 10 | HIPAA Compliance & Minor Patient Privacy Rules | Regulatory compliance |
| 11 | Pediatrics Billing for Different Practice Settings | Solo, group, FQHC, hospital |
| 12 | Technology & EHR Integration in Pediatrics Billing Services | Systems & tools |
| 13 | KPIs Every Pediatric Practice Should Track | Revenue analytics |
| 14 | Outsourced vs. In-House Pediatrics Medical Billing Services | Decision framework |
| 15 | FAQs: Pediatrics Billing Services | Top 10 questions answered |

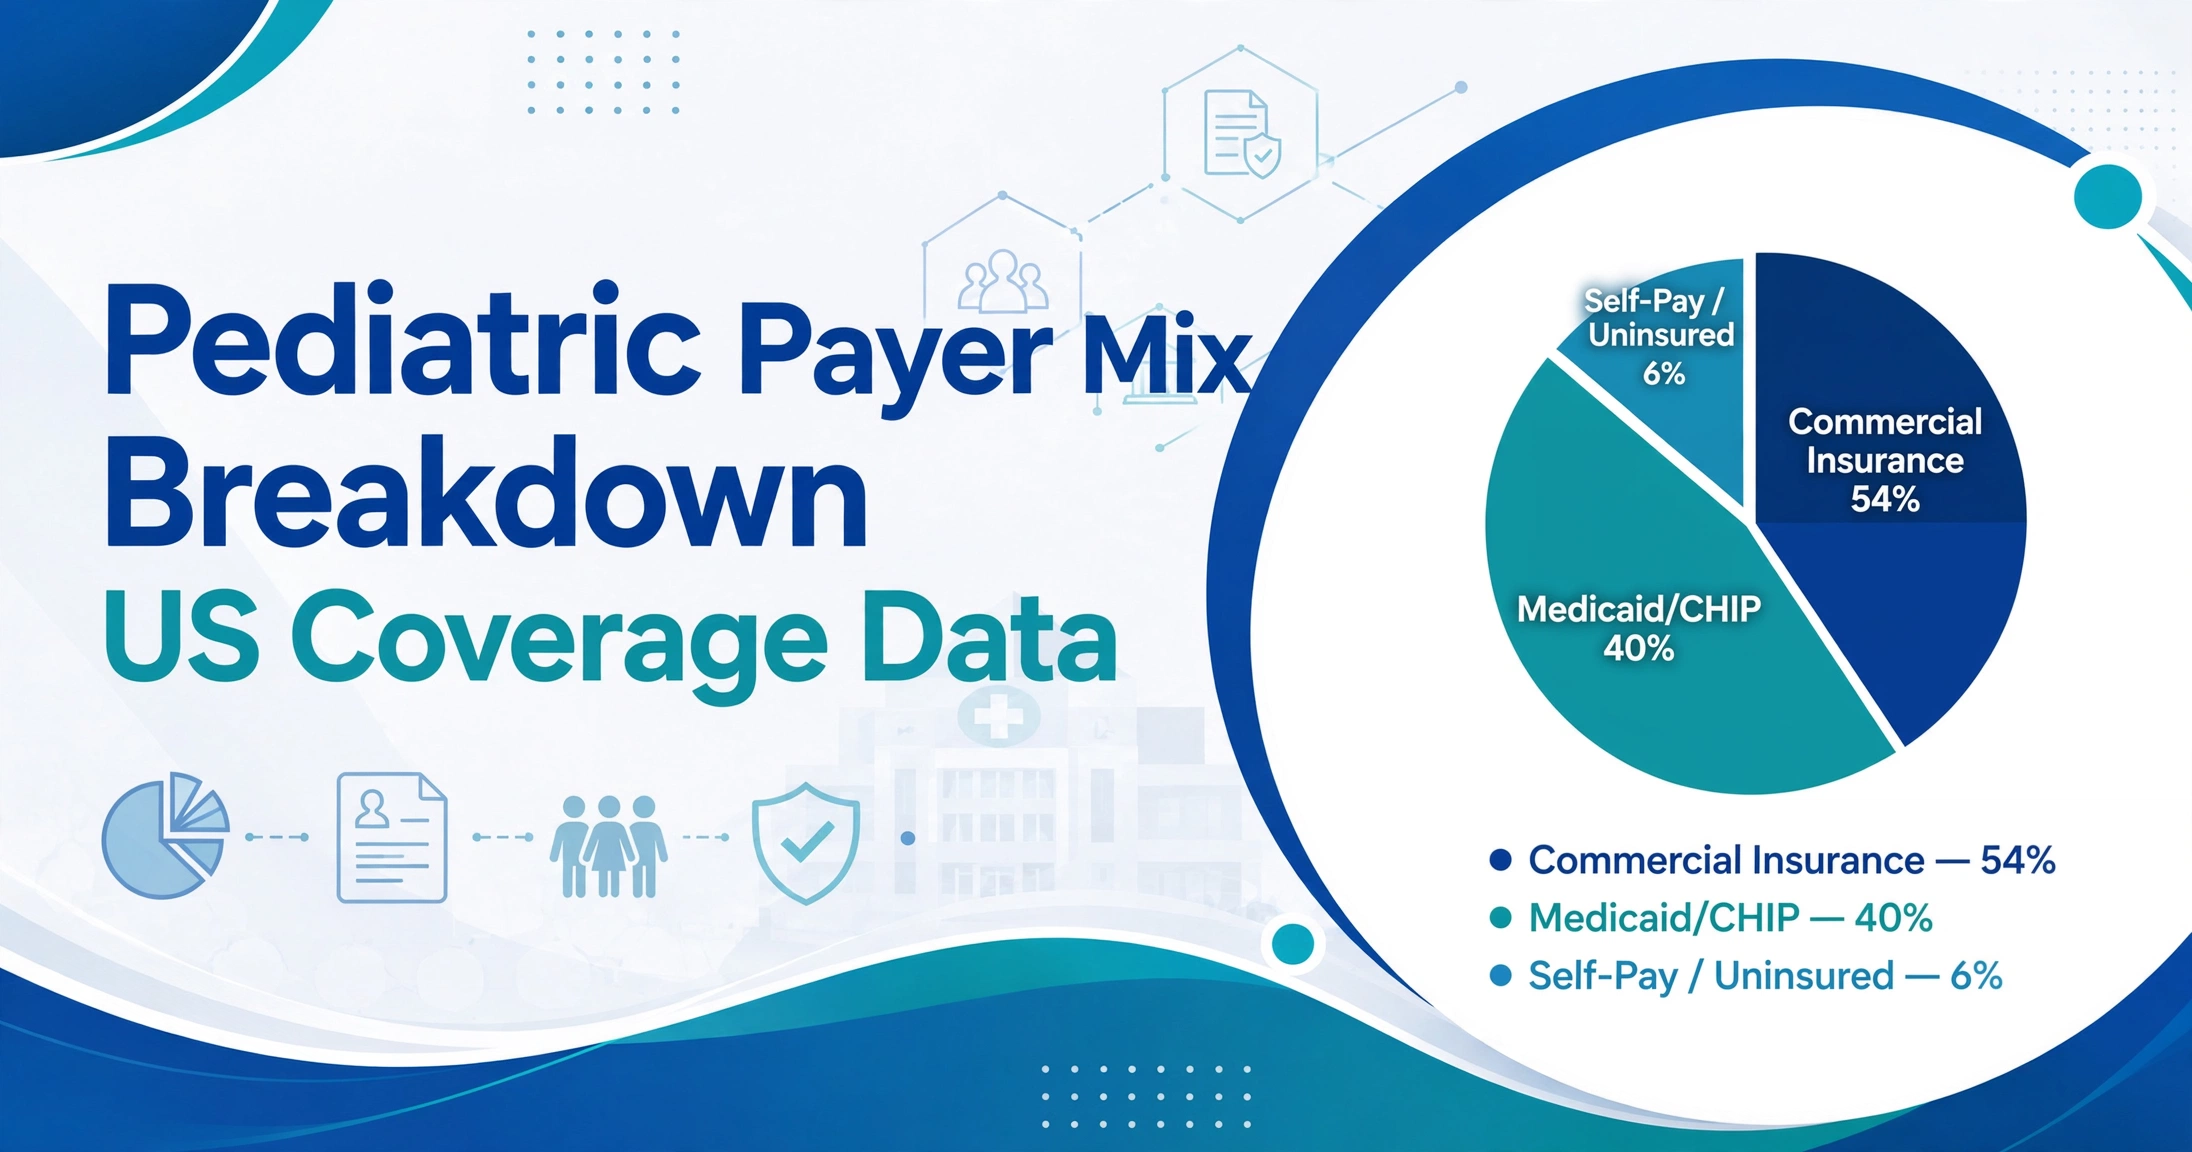
Pediatrics medical billing is the specialized process of translating the clinical services your pediatric practice delivers into accurate insurance claims from newborn care and well-child visits to chronic disease management and behavioral health screenings. If you run a pediatric practice in the United States, you’re dealing with a payer mix that’s unlike any other specialty: Medicaid and CHIP often cover 40–60% of your patient population, commercial payers have their own preventive care rules, and the AAP’s well-child visit schedule drives a large share of your annual revenue.
Getting pediatrics medical billing right isn’t just about revenue, it’s about keeping your practice financially stable so you can keep serving children and families in your community. According to the American Academy of Pediatrics (AAP), pediatric practices face some of the most complex billing environments in primary care, largely because of their heavy reliance on government payers with evolving EPSDT and CHIP requirements.
Our this guide covers everything a US pediatrician, practice administrator, or billing manager needs to know: the CPT codes, Medicaid billing rules, immunization billing, denial management, compliance requirements, and how to evaluate pediatrics billing services vendors.
⚠️ Key Industry Stat |
The Kaiser Family Foundation reports that Medicaid and CHIP covered approximately 41% of all children in the United States as of 2023, making government payer expertise the single most important factor in pediatrics medical billing performance. |
Many billing companies claim they can handle pediatric practices, but generalist billing teams routinely miss revenue that pediatrics-specific expertise would capture. Here’s what makes your pediatrics medical billing services genuinely complex:
Medicaid/CHIP dominance, state-specific rules, fee schedules, and EPSDT mandates require constant payer policy monitoring.
Well-child visit bundling rules vary by payer, what’s billable separately on a commercial plan may be bundled under Medicaid.
Vaccine administration billing, VFC (Vaccines for Children) program rules, administration code stacking, and vaccine product coding require precise workflow.
Age-specific coding, many CPT codes and ICD-10 codes have pediatric-specific age restrictions that generic billing systems miss.
Developmental and behavioral screening billing (M-CHAT, MCHAT-R, CRAFFT, PHQ-A) has payer-specific coverage rules.
Minor patient consent and confidentiality rules create unique HIPAA and billing compliance challenges.
Newborn care billing in hospital settings has complex same-day service and global period rules.
Coordination of benefits with Medicaid as secondary payer requires specialized claim sequencing knowledge.
rates
Accurate CPT code selection is the foundation of every successful pediatrics billing claim of your practice. The following table covers the core CPT code families that drive pediatric practice revenue:
| CPT Code / Range | Service Category | Description | Key Billing Notes |
|---|---|---|---|
| 99381–99385 | New Patient Preventive (Office) | Well-child visits, newborn through 18+ years by age group | Age must match code; 99381=infant, 99382=1–4 yrs, 99383=5–11 yrs, 99384=12–17 yrs, 99385=18+ yrs |
| 99391–99395 | Established Patient Preventive | Annual well-child visits, established patients by age group | Most frequently billed preventive codes in pediatrics; payer prior auth rarely required |
| 99202–99215 | Office/Outpatient E/M (New/Est) | Sick visits, follow-up, chronic disease management | Medical Decision Making (MDM) or Time-based documentation required post-2021 guidelines |
| 90460–90461 | Immunization Administration | Administration of vaccine with counseling (per component) | 90460 = first component; 90461 = each additional; counseling must be documented |
| 90471–90474 | Immunization Administration (No Counseling) | Vaccine administration without physician counseling | Used when counseling not provided or not documented |
| 90700–90749 | Vaccine Products | Individual vaccine product codes (DTaP, MMR, Varicella, etc.) | VFC vaccines billed at $0; privately purchased vaccines billed at cost |
| 96110 | Developmental Screening | Standardized developmental screening with scoring and documentation | M-CHAT, ASQ; once per visit per payer; Medicaid coverage varies by state |
| 96127 | Brief Emotional/Behavioral Assessment | Standardized instrument (PHQ-A, CRAFFT, SCARED) | Check payer LCD for coverage; limit per visit varies |
| 99460–99463 | Newborn Care (Hospital) | Initial and subsequent newborn hospital care | Global period rules apply; same-day discharge has special codes (99463) |
| 99221–99223 | Initial Hospital Care | Admission E/M for pediatric inpatient admission | Documentation must support level selected |
| 99281–99285 | Emergency Department Visits | ED E/M for pediatric emergencies | Level driven by MDM and presenting problem severity |
| 99051 | After-Hours Service | Services provided after normal business hours | Billable supplement to E/M; document time and circumstance |
�� Tip: Well-Child Visit CPT Code Selection |
The age of the patient on the DATE OF SERVICE determines which preventive visit code (99381–99395) you can use, not the age at which they were last seen. A child who turns 12 between visits crosses from 99393 to 99394 at that birthday. |
Document separately billable services performed during a well-child visit with modifier -25 on the E/M code when a separately identifiable sick visit problem is addressed on the same day. Without -25, commercial payers will bundle the E/M. |
Medicaid managed care plans often have different preventive visit billing rules than fee-for-service Medicaid. Always verify current plan-specific policies, as they update annually. |
Our comprehensive pediatrics billing service covers your entire revenue cycle, not just submitting claims. Here’s what a best-in-class pediatrics billing services partner delivers:
| Service Component | What It Includes | Why It Matters for Pediatrics |
|---|---|---|
| Charge Capture & Code Review | Visit-by-visit CPT/ICD-10 review, modifier assignment, fee schedule mapping | Prevents well-child bundling errors and missed add-on codes |
| Eligibility Verification | Real-time insurance verification before every visit; Medicaid/CHIP status check | Medicaid eligibility changes monthly, same-day verification is essential |
| Claims Submission | Electronic claims via clearinghouse; EPSDT supplement form submission | Accelerates payment; EPSDT forms required for many Medicaid preventive services |
| Prior Authorization Management | Pre-auth for referrals, behavioral health, procedures | Reduces denials for specialist referrals and mental health services |
| Immunization Billing | VFC vs. private stock tracking, 90460/90471 administration code assignment | Incorrect VFC/private mix-up is a major compliance and billing error |
| Denial Management | Root-cause analysis, appeal workflows, payer follow-up | Recovers denied preventive and sick visit revenue |
| Medicaid/CHIP Reconciliation | State-specific EPSDT billing, MCO vs. FFS claim routing | Ensures you're billing the right entity and using correct forms |
| Patient Billing & Collections | Statement generation, sliding scale/FQHC documentation, payment plans | Pediatric patients often have self-pay or high-deductible commercial coverage |
| Compliance & Audit Support | OIG monitoring, Medicaid RAC audit response, documentation review | Pediatric Medicaid is a frequent audit target |
| Reporting & Analytics | Monthly KPI dashboards, denial trending, payer performance by plan | Data-driven practice management |
ICD-10-CM diagnosis codes in pediatrics billing establish medical necessity, define the encounter type, and determine payer coverage. Pediatrics has a rich set of age-specific and condition-specific codes that must be mapped precisely:
| ICD-10 Code | Description | Pediatrics Billing Context |
|---|---|---|
| Z00.00 / Z00.01 | Encounter for general adult exam without/with abnormal findings | Well-child visits (use Z00.1xx for children under 29 days) |
| Z00.110 / Z00.111 | Health exam for newborn under 8 days old | Initial newborn assessment; hospital and office settings |
| Z00.121 / Z00.129 | Routine child health exam with/without abnormal findings | Well-child visits ages 1–17; most common preventive code in pediatrics |
| Z23 | Encounter for immunization | Vaccine-only visits; combine with vaccine CPT codes |
| J06.9 | Acute upper respiratory infection, unspecified | Most common sick visit diagnosis in pediatrics |
| J02.9 / J03.90 | Acute pharyngitis / Acute tonsillitis | Strep throat presentation; pair with strep test CPT |
| H66.90 | Otitis media, unspecified | Ear infection — high volume in toddler age group |
| F90.0–F90.9 | ADHD — predominantly inattentive/hyperactive/combined | Growing share of pediatric E/M visits; requires behavior rating scale documentation |
| F41.1 | Generalized anxiety disorder | Adolescent behavioral health; pair with 96127 screening codes |
| E11.9 / E10.9 | Type 2 / Type 1 diabetes mellitus | Pediatric chronic disease management visits |
| Z13.88 | Encounter for screening for disorder due to exposure to contaminants | Lead screening — required for Medicaid EPSDT children ages 1–2 |
| R62.51 | Failure to thrive (child) | Growth concern visits; triggers nutritional counseling billing |
No section of this guide is more important for most US pediatric practices than Medicaid and CHIP billing. With 41% of American children covered by these programs, mastering government payer billing is directly tied to your practice’s financial survival.
EPSDT (Early and Periodic Screening, Diagnostic, and Treatment) is the Medicaid program’s children’s health benefit, and it’s legally required to cover any medically necessary service for a child, even if it’s not in the state’s standard Medicaid adult benefit package. As a pediatrician, understanding EPSDT billing rules is essential:
EPSDT covers preventive screenings at AAP-recommended intervals regardless of Medicaid state plan limitations.
If a screening identifies a need, EPSDT mandates that treatment be covered you must document the identified need and the plan.
EPSDT supplemental forms (e.g., CMS-1500 with modifier EP) are required by many state Medicaid programs.
Lead screening is an EPSDT-required service for children ages 12–24 months and 24–72 months in high-risk areas.
Vision, hearing, and dental referrals identified at EPSDT visits must be documented and tracked.
| Payer Type | Billing Form | Key Pediatrics Rules | Resource |
|---|---|---|---|
| Medicaid Fee-for-Service | CMS-1500 / State-specific | EPSDT modifier, state fee schedule, monthly eligibility check | medicaid.gov/state-overviews |
| Medicaid Managed Care (MCO) | CMS-1500 per plan rules | Each MCO has own prior auth and referral rules; verify per plan | Plan-specific provider manual |
| CHIP (Children's Health Insurance Program) | CMS-1500 | Lower cost-sharing than Medicaid; some states use commercial-style benefits | medicaid.gov/chip/index.html |
| Medicare (rare in pediatrics) | CMS-1500 | Applies to children with disabilities on Medicare; follow standard Medicare rules | cms.gov/medicare |
| Commercial / Private Insurance | CMS-1500 | Preventive vs. sick visit copay rules; ACA preventive services coverage mandate | healthcare.gov/coverage/preventive-care-benefits |
Tip: Medicaid Eligibility Verification in Pediatrics |
Medicaid eligibility for children changes every month, a patient who was covered last visit may have lapsed coverage today. Verify eligibility on the date of service, not just at registration. |
Many states have an online portal for real-time Medicaid eligibility verification. Set up your front desk workflow to check every child’s Medicaid status at check-in. |
When Medicaid is the secondary payer (child has commercial primary), bill the commercial insurer first, then cross-over to Medicaid for the patient responsibility amount. Do NOT bill Medicaid directly without first billing primary. |
Well-child visits are the revenue backbone of most pediatric practices, and they’re also the most frequently miscoded and underbilled category of services. Let’s break down best practices for preventive care billing in pediatrics medical billing services:
| Age Group | AAP Recommended Visit | CPT Code (New) | CPT Code (Est.) | Key Services to Bill Separately |
|---|---|---|---|---|
| Newborn (3–5 days) | First office visit | 99381 | N/A | Hearing screen (92587), bilirubin check |
| 1 month | Well-child | 99381 | 99391 | Development screening (96110) |
| 2 months | Well-child + vaccines | 99381 | 99391 | Immunizations (90460 x components) |
| 4 months | Well-child + vaccines | 99381 | 99391 | Immunizations, development screening |
| 6 months | Well-child + vaccines | 99381 | 99391 | Lead risk assessment, fluoride varnish (D1206) |
| 9 months | Well-child | 99382 | 99392 | Development screen (96110), ASQ |
| 12 months | Well-child + vaccines | 99382 | 99392 | Lead test (83655), anemia screen (85018) |
| 15 months | Well-child + vaccines | 99382 | 99392 | M-CHAT screening (96110), immunizations |
| 18 months | Well-child + vaccines | 99382 | 99392 | M-CHAT-R/F (96110), developmental eval |
| 2–5 years | Annual well-child | 99382/99383 | 99392/99393 | Development/autism screen, vision screen |
| 6–11 years | Annual well-child | 99383 | 99393 | BMI counseling, ADHD screening (96127) |
| 12–17 years | Annual well-child | 99384 | 99394 | Depression screen (96127), STI screen, CRAFFT |
Immunization billing is one of the most financially significant, and most frequently mis-billed — areas of pediatrics medical billing. The combination of VFC (Vaccines for Children) program rules, administration code selection, and counseling documentation requirements creates a billing minefield that costs pediatric practices real revenue every year.
| CPT Code | Description | When to Use | Key Billing Rule |
|---|---|---|---|
| 90460 | Immunization admin w/ counseling — first component | Any age <18 when physician/QHP provides counseling | Must document counseling provided by MD/DO/NP/PA, not just staff |
| 90461 | Immunization admin w/ counseling — each add'l component | Each antigen beyond the first (e.g., DTaP = 3 antigens) | Bill once per additional antigen, not per additional vaccine |
| 90471 | Immunization admin w/o counseling — first injection | Adults or when counseling not provided/documented | More commonly used in adult medicine; less appropriate for pediatrics |
| 90472 | Immunization admin w/o counseling — each additional | Each additional injection when no counseling | Lower reimbursement than 90460/90461 — use counseling codes when appropriate |
| 90473 | Immunization admin — first intranasal/oral | FluMist administration | Separate code from injection administration |
| 90474 | Immunization admin — each additional intranasal/oral | Additional intranasal/oral vaccines | Less commonly used |
⚠️ VFC Program Billing Alert |
Vaccines provided through the Vaccines for Children (VFC) program are free to the practice, you may not bill for the vaccine product itself. You may only bill the administration code (90460/90461 or 90471/90472). Billing a VFC vaccine product cost to Medicaid is a Federal False Claims Act violation. Track your VFC vs. private stock inventory rigorously and ensure your LIS/EHR distinguishes the two at point of administration. |
Tip: Maximizing Immunization Administration Revenue |
A single well-child visit with a 5-antigen combination vaccine (e.g., Pediarix — DTaP + HepB + IPV) generates 90460 + 90461 x 4 in administration codes when counseling is documented. That’s 5 billable units from one vaccine. Ensure your EHR auto-calculates antigen counts. |
Many Medicaid plans reimburse 90460/90461 at higher rates than 90471/90472. If your physicians are providing counseling (and documenting it), using the correct codes adds meaningful revenue per visit. |
Some commercial payers bundle immunization administration into the well-child visit payment. Know your payer-by-payer rules — what you can bill separately on Blue Cross may be bundled under Aetna. |
Denial management is where your pediatric practice recovers the most lost revenue. Here are the denials that hit pediatric practices hardest and the proven solutions:
| Denial Type | Root Cause | Fix / Prevention |
|---|---|---|
| Well-child bundled with sick visit E/M | Missing modifier -25 on same-day sick E/M | Append modifier -25 to E/M when a separately identifiable problem addressed; document medical necessity |
| Immunization counseling denied | 90460 billed but counseling not documented | Mandate counseling documentation in EHR at point of care; train staff on documentation requirements |
| Medicaid eligibility at DOS | Patient's Medicaid lapsed; billed wrong MCO | Verify Medicaid eligibility on date of service via state portal; update payer info at every visit |
| Developmental screening denied | 96110/96127 billed more than once per visit per payer rules | Load payer-specific frequency limits into billing system; track per-patient per-year count |
| VFC vaccine product billed to Medicaid | Billing vaccine cost for VFC stock | Separate VFC vs. private stock in EHR; audit vaccine billing monthly |
| Age mismatch on preventive code | CPT preventive code doesn't match patient age | Implement EHR age-based code validation; train coders on age cutoffs for 99381–99395 |
| Prior auth missing for referral | Specialist referral made without Medicaid MCO authorization | Build PA workflow into referral process; track auth numbers before patient seen by specialist |
| Timely filing exceeded | Claim not submitted within payer's deadline | Set 30-day submission alerts; Medicaid timely filing windows vary 90–365 days by state |
| EPSDT form missing | State Medicaid requires supplemental EPSDT form not submitted | Identify state-specific EPSDT form requirements; automate form generation at well-child visits |
Pediatrics practices face unique HIPAA and privacy compliance challenges that simply don’t exist in adult medicine. When your patients are minors, the intersection of parental rights, minor consent laws, and insurance billing creates a compliance landscape you need to navigate carefully.
✅ HIPAA Compliance Checklist for Pediatrics Billing |
Execute current Business Associate Agreements (BAAs) with all billing vendors who access PHI |
Understand your state’s minor consent laws adolescents may have rights to confidential services (STI, contraception, mental health, substance abuse) that parents cannot access via EOBs |
Implement protocols to handle Explanation of Benefits (EOB) suppression when confidential minor services are billed to a parent’s insurance |
Train front desk and billing staff on when to release billing information to parents vs. patients |
Audit access logs in your billing system quarterly; restrict access to minimum necessary information |
Document patient authorizations for any disclosure beyond treatment, payment, and operations |
Pediatrics medical billing services must be tailored to your practice setting. The rules, forms, and payer relationships differ significantly across these environments:
| Practice Setting | Billing Model | Key Pediatrics Billing Considerations |
|---|---|---|
| Private/Independent Pediatric Practice | CMS-1500; mix of Medicaid, CHIP, commercial | Highest billing complexity; most dependent on specialized pediatrics billing services |
| Pediatric Group Practice | CMS-1500; group NPI billing; provider credentialing per payer | Ensure all pediatricians are credentialed with Medicaid MCOs; group vs. individual NPI rules |
| Federally Qualified Health Center (FQHC) | Prospective Payment System (PPS) per-visit rate | FQHC PPS rate covers most services; supplemental billing rules apply for some vaccines/labs |
| Hospital-Based Pediatric Clinic | Professional billing (CMS-1500) + facility (UB-04) | Split billing between professional group and hospital; avoid duplicate billing |
| Pediatric Emergency Department | ED E/M codes 99281–99285; facility billing separate | Level assignment based on MDM; observation vs. inpatient admission rules |
| School-Based Health Center | Medicaid school-based billing; state-specific rules | Parental consent for billing required; EPSDT frequently applies |
| Telehealth Pediatrics | Standard CPT with GT/95 modifier; place of service 02/10 | Payer policies on pediatric telehealth vary; Medicaid telehealth coverage varies by state |
The technology stack powering your pediatrics billing services is as important as the human expertise behind it. Here’s what an optimized pediatric billing technology environment looks like:
| Technology Layer | Purpose in Pediatrics Billing | Leading Options |
|---|---|---|
| EHR / Practice Management | Well-child visit templates, immunization tracking, CPT auto-suggestion, EPSDT forms | Epic, Athenahealth, eClinicalWorks, Modernizing Medicine |
| Immunization Information System (IIS) | State registry integration for VFC tracking and immunization record verification | State-specific IIS (e.g., CHIRP, ImmTrac2, VOMS) |
| Clearinghouse | Electronic claim submission, real-time eligibility, ERA processing | Change Healthcare, Availity, Office Ally, Waystar |
| Medicaid Provider Portals | Eligibility verification, prior auth, claim status for Medicaid/MCO plans | State Medicaid portal + each MCO's provider portal |
| Denial Management Software | Denial categorization, appeal workflow, root cause tracking | Waystar, Veradigm, RCM platform reporting modules |
| Analytics / Reporting | Payer mix analysis, denial trending, vaccine revenue by CPT | Built-in PM reports, Power BI, Tableau |
Tip: EHR-Billing Integration for Pediatrics |
Your EHR’s well-child visit template should auto-populate the age-appropriate preventive CPT code, the AAP-recommended screening list (with documentation prompts), and the appropriate immunization administration codes based on vaccines given. |
Set up your EHR to auto-flag when a child’s last well-child visit was more than 12 months ago, this creates an outreach opportunity and ensures you’re not missing annual preventive revenue. |
Integrate your state’s Immunization Information System (IIS) directly with your EHR to auto-verify vaccine history before administering duplicates and to maintain accurate VFC vs. private stock records. |
You can’t improve your pediatrics billing performance without measuring it. These are the KPIs that matter most for pediatric practice revenue cycle management:
| KPI | Definition / Formula | Benchmark Target |
|---|---|---|
| Days in AR | Total AR ÷ Average daily charges | < 35 days |
| First Pass Resolution Rate | Claims paid on first submission ÷ Total claims submitted | > 95% |
| Denial Rate | Denied claims ÷ Total claims submitted | < 5% |
| Clean Claim Rate | Claims accepted without edits ÷ Total submitted | > 98% |
| Medicaid Collection Rate | Medicaid collections ÷ Net Medicaid charges | > 92% |
| Well-Child Visit Capture Rate | WCV visits billed ÷ WCV visits eligible (by schedule) | > 80% of eligible patients seen annually |
| Immunization Revenue per Visit | Total vaccine admin revenue ÷ Total visits with vaccines | Benchmark against your payer mix; track monthly trend |
| Charge Lag | Days from patient encounter to claim submission | < 48 hours |
| Underpayment Rate | Claims paid below contracted rate ÷ Total paid claims | < 2% |
| EPSDT Compliance Rate | EPSDT screens completed ÷ EPSDT-eligible visits | > 90% (Medicaid quality metric) |
Should you keep billing in-house or partner with a specialized pediatrics billing services company? Here’s the honest comparison every pediatric practice administrator needs to see:
| Factor | In-House Billing | Outsourced Pediatrics Billing Services |
|---|---|---|
| Startup Cost | High staff, EHR/PM setup, training, compliance infrastructure | Low percentage of collections or flat monthly fee |
| Ongoing Cost | Salaries, benefits, PTO coverage, software licenses, coder training | Predictable % of revenue; no HR overhead for billing staff |
| Medicaid Expertise | Dependent on staff experience; hard to maintain across 50+ MCO plan rules | Specialized vendors maintain current Medicaid/MCO policy knowledge |
| Immunization Billing Accuracy | Requires ongoing training on VFC rules, antigen counting, payer bundling | Pediatrics billing specialists handle immunization coding as core competency |
| Scalability | Difficult — hiring lags patient volume growth | Scales with your volume immediately |
| EPSDT & Compliance | Requires internal audit program and state policy monitoring | Typically included; specialists track state Medicaid and EPSDT updates |
| Revenue Performance | Variable — billing expertise gaps cost revenue | Consistent — performance tracked via SLA with reporting accountability |
| Best For | Large multi-physician groups with dedicated billing teams | Solo pediatricians, small-medium groups, practices on Medicaid-heavy payer mix |
Tip: What to Ask a Pediatrics Billing Vendor |
Ask how many pediatric practices they currently serve and what their average Medicaid collection rate is across those clients. |
Request a sample denial analysis report, it should break down denials by CPT code, denial reason code, and payer. If they can’t produce this, they can’t manage your denials effectively. |
Ask specifically about their VFC billing compliance process how do they ensure you’re never billing VFC product costs to Medicaid? |
Verify they have certified coders (CPC or CPC-P through AAPC) with documented pediatrics coding experience, not just general primary care billing. |
We’ve compiled the most important external resources for US pediatrics billing compliance, coding accuracy, and Medicaid policy. Bookmark these for your team:
| Resource | Organization | URL |
|---|---|---|
| Coding at the AAP | American Academy of Pediatrics | aap.org/en/practice-management/coding-at-the-aap/ |
| Bright Futures Periodicity Schedule | AAP | aap.org/en/practice-management/bright-futures/ |
| EPSDT Program Information | CMS / Medicaid.gov | medicaid.gov/medicaid/benefits/early-and-periodic-screening-diagnostic-and-treatment/ |
| CHIP Program Resources | Medicaid.gov | medicaid.gov/chip/index.html |
| VFC Program Information | CDC | cdc.gov/vaccines/programs/vfc/index.html |
| CMS Physician Fee Schedule | CMS (Medicare) | cms.gov/medicare/physician-fee-schedule/search |
| ICD-10-CM Official Guidelines | CMS / CDC | cms.gov/medicare/coding-billing/icd-10-codes/icd-10-cm-documentation |
| NCCI Policy Manual | CMS / NCCI | cms.gov/medicare/coding-billing/national-correct-coding-initiative-edits |
| OIG Work Plan | HHS Office of Inspector General | oig.hhs.gov/reports-and-publications/workplan/index.asp |
| HIPAA for Individuals | HHS Office for Civil Rights | hhs.gov/hipaa/for-individuals/index.html |
| MGMA DataDive Benchmarks | Medical Group Management Assoc. | mgma.com/data/benchmarking-data/mgma-datadive |
| State Medicaid Overviews | Medicaid.gov | medicaid.gov/state-overviews/index.html |
The most revenue-critical CPT codes in pediatrics billing are the preventive visit codes (99381–99395 for well-child visits by age group), immunization administration codes (90460/90461 for counseling-based administration), and the office E/M codes (99202–99215) for sick visits and chronic disease management. Developmental screening codes (96110, 96127) are increasingly important as AAP recommendations expand screening requirements. For practices with hospital privileges, newborn care codes (99460–99463) also represent significant revenue
Medicaid pediatric billing operates through two channels: fee-for-service (FFS) Medicaid billed directly to the state, and Medicaid Managed Care Organizations (MCOs) billed to private insurance companies that contract with the state. Most states have shifted to MCO-dominant Medicaid, which means you need to be credentialed with each MCO individually. Every Medicaid-covered child is entitled to EPSDT services — learn your state’s EPSDT billing requirements at Medicaid EPSDT. Eligibility must be verified on every date of service, as Medicaid coverage for children can change monthly
Yes, but only if a separately identifiable sick or problem-focused service is performed and documented beyond the scope of the well-child visit. You must append modifier -25 to the E/M code (sick visit CPT) to indicate to the payer that a significant, separately identifiable service was provided on the same day as a preventive service. Without modifier -25, the sick E/M will be bundled into the preventive visit payment and denied. Not all payers allow this combination Medicaid plans vary, and some commercial plans prohibit same-day preventive plus problem-focused billing entirely. Know your payer rules before billing
VFC (Vaccines for Children) vaccines are provided free to your practice by the CDC through your state health department. You may NEVER bill the vaccine product cost to Medicaid, CHIP, or any payer for a VFC vaccine, doing so is a Federal False Claims Act violation. For VFC vaccines, you bill only the administration codes (90460/90461 or 90471/90472). For privately purchased vaccines given to commercially insured patients or non-VFC-eligible Medicaid patients, you bill both the vaccine product CPT code and the administration code. Your EHR/inventory system must clearly separate VFC stock from private stock at the point of administration. For full VFC program rules, visit CDC VFC Program
EPSDT, Early and Periodic Screening, Diagnostic, and Treatment — is the Medicaid program’s comprehensive children’s health benefit. It legally requires states to cover all medically necessary services for Medicaid-enrolled children, even if those services aren’t part of the adult Medicaid benefit package. For billing purposes, EPSDT means: (1) you can bill for a wide range of preventive screenings and treatment services under Medicaid, (2) many states require you to submit a supplemental EPSDT form alongside your claim, (3) documenting identified health needs at the well-child visit and the plan to address them is both a clinical and billing requirement. Missing EPSDT documentation and forms is a leading cause of preventive visit denials in Medicaid billing
Get a free assessment from our billing experts
